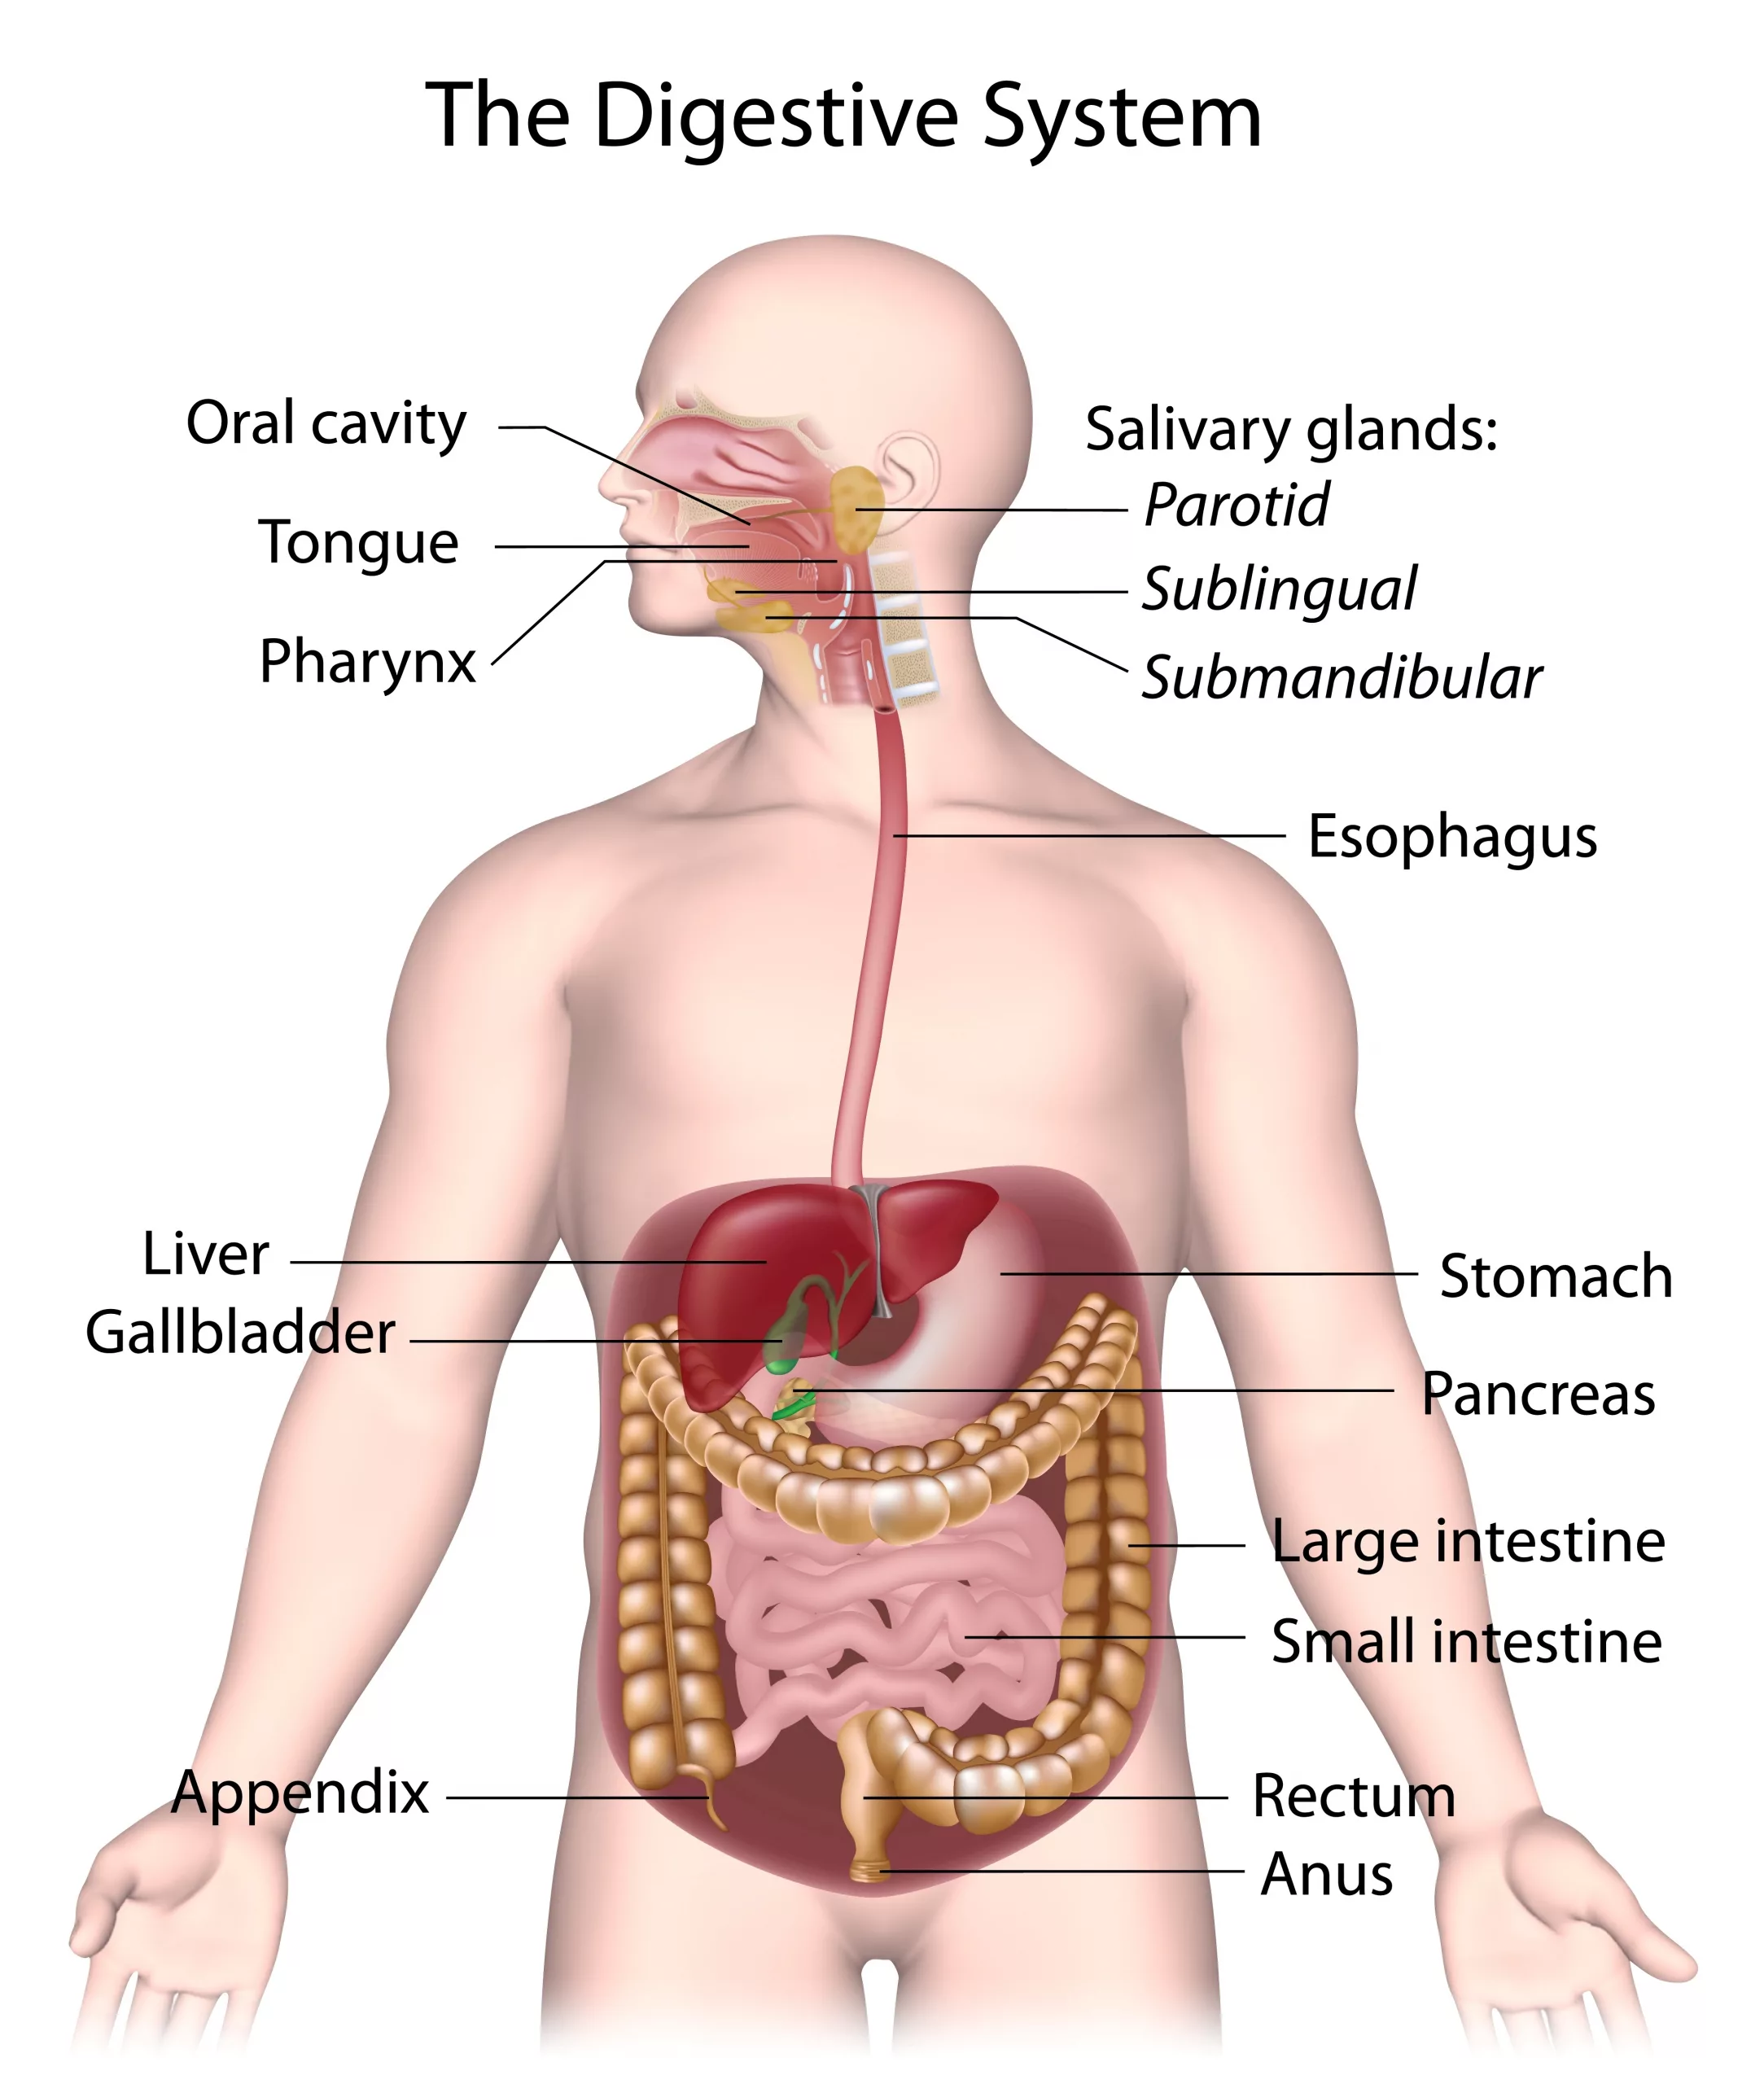
‘The human digestive system consists of the alimentary canal [the gut] and its associated glands, the salivary glands, the liver and the pancreas. The alimentary canal begins at the mouth and ends at the anus. Between the two openings is a long convoluted tube organised into several distinct regions.’
(Boyle and Senior, 2008: 131).
The Short Answer
The digestive system is:
the ‘alimentary canal and its associated glands, the salivary glands, the liver and the pancreas.’ (Boyle and Senior, 2008: 131)
The Extended Answer
Within the alimentary canal are:
The mouth, including the tongue and teeth.
The oesophagus, which ‘carries food from the mouth to the stomach’
The stomach, ‘a muscular bag or sac that stores food’
The small intestine, which is where most digestion and absorption occurs. It includes the:
duodenum
ileum
The large intestine, including the:
appendix
colon, ‘whose main function is to absorb water’
rectum
The anus
(Boyle and Senior, 2008: 130-131)
The digestive system is therefore consisted of all of the above as well as the liver ‘and its adjuncts – the gallbladder and bile ducts’ (Keeton et al, 2020), pancreas, and the salivary glands.
Of course, each component has its own functions and parts. As such, this answer could be extended even further.
References
Boyle, M. And Senior, K. 2008. Human Biology, Third Edition, Collins: London
Collison, P. et al, 2001. Nelson Modular Science 1, Nelson Thornes: Cheltenham
Keeton, W.T. et al, 2020. Human Digestive System, Available Online: https://www.britannica.com/science/human-digestive-system (Accessed 13/09/20)
Digestive system with salivary glands (licensed Adobe image)
This post is based on the NICE Clinical Guidelines, 2014. One part of their guidelines was in turn updated in 2019.
This post shows the key points and quotes as they relate to frontline ambulance staff; anything not relevant has not been included, but you may read more by following the link to the guidelines here.
Remember to read our disclaimer before putting into practice anything you see, hear, or read here. Also remember to check your local guidelines and the scope of practice for your role before putting any of this into practice.
Article 999: Simplifying the Long Stuff; Presenting the Relevant Stuff; Refreshingyou on the Important Stuff.
www.article999.co.uk
Definition of Head Injuries
‘any trauma to the head other than superficial injuries to the face.’ p6
National Institute for Health and Care Excellence [NICE], 2014: 6
Statistics
‘Head injury is the commonest cause of death and disability in people aged 1-40 years in the UK.’
NICE, 2014: 6
‘The incidence of death from head injury is low, with as few as 0.2% of all patients attending emergency departments with a head injury dying as a result of this injury.’
NICE, 2014: 6
‘the majority of fatal outcomes are in the moderate (GCS 9-12) or severe (GCS 8 or less) head injury groups’
NICE, 2014: 6
When might adults need to attend A&E for a CT head scan following a head injury?
‘For adults who have sustained a head injury and have any of the following risk factors’
Reduced GCS, ‘less than 13’ initially, or ‘less than 15 at 2 hours after the injury on assessment in the emergency department’*
suspected skull fracture of any type
‘post-traumatic seizure’
Neurological deficit
‘More than 1 episode of vomiting’
–> This should happen within one hour of identifying the situation.
(NICE, 2014: 10)
*Consider ‘the pre-injury baseline GCS may be less than 15. Establish this where possible’ (NICE, 2014: 19).
If the patient is on anticoagulants and has none of the above, they should have a CT head ‘within 8 hours of the injury’. (NICE, 2014: 12)
When might adults need to attend A&E for a CTcervical spinefollowing a head injury?
‘The patient has been intubated’
‘The patient is having other body areas scanned for head injury
‘…there is clinical suspicion of cervical spine injury and any of the following apply:
=> 65
‘dangerous mechanism of injury’
neuro deficit
‘paraesthesia in the upper or lower limbs’
(NICE, 2014: 13)
When might children need to attend hospital for a CT head scanfollowing a head injury?
Any of:
‘Suspicion of non-accidental injury’
‘Post-traumatic seizure but no history of epilepsy’
Reduced GCS <14 initially, <15 2 hours later
For under 1 year olds, Reduced GCS <15 on the paediatric scale
Suspected skull fracture of any type
Neuro deficit
For under 1 year olds, ‘presence of bruise, swelling or laceration of more than 5 cm on the head’
(NICE, 2014: 11)
If a child has ‘more than one’ of these, he/she should have a CT scan within an hour:
‘Loss of consciousness lasting more than 5 minutes (witnessed)’
‘Abnormal drowsiness’
Vomiting x3 or more episodes
‘Dangerous mechanism of injury (high-speed road traffic accident either as pedestrian, cyclist or vehicle occupant, fall from a height of greater than 3 metres, high-speed injury from a projectile or other object)’
‘Amnesia […] lasting more than 5 minutes’
(NICE, 2014: 11)
Note: If the child has just one of these, he/she ‘should be observed for a minimum of 4 hours after the head injury’ and if he/she then develops more of the above, a CT is warranted. (NICE, 2014: 12)
The rules regarding CT cervical spine scans are different in children, compared to adults, due to the risk of radiation to their thyroid.
‘Consider or suspect abuse as a contributory factor to or cause of head injury in children’ (NICE, 2014: 7)
For what other reasons should an adult or child with a head injury attend A&E?
loss of consciousness
‘Amnesia for events before or after the injury’
‘Persistent headache since the injury’
‘Any vomiting episodes since the injury’ – but NICE advise considering the causes of single vomiting episodes in those under 12
‘Any seizure since the injury’
‘Any previous brain surgery’
‘A high-energy head injury’
‘Any history of bleeding and clotting disorders’
Anticoagulants
‘Current drug or alcohol intoxication’
Safeguarding issues
‘Continuing concern by the professional about the diagnosis’ (NICE, 2014: 17-18)
And:
Patients who, 48 hours later, have ‘any persistent complaint relating to the initial head injury’ (NICE, 2014: 23)
Also, ‘depending on judgement of severity:’
‘irritability or altered behaviour’
Other ‘Visible trauma to the head […] of concern to the professional’
‘No one is able to observe the injured person at home’
‘Continuing concern by the injured person or their family or carer about the diagnosis’ (NICE, 2014: 18)
What else should I consider in my assessment and treatment of a patient with a head injury?
For adults, NICE recommends ‘managing their care according to clear principles and standard practice’ as in the ATLS and PHTLS courses, and the JRCALC for adults, and the APLS and PHPLS courses for children. There are others referenced, but Article 999 has included the most relevant here. (NICE, 2014: 19-20)
‘Manage pain effectively because it can lead to a rise in intracranial pressure’ (NICE, 2014: 21)
‘Ascribe depressed conscious level to intoxication only after a significant brain injury has been excluded’ (NICE, 2014: 21-22)
Pre-alert patients with a reduced GCS, especially of <8. They will most likely need anesthetist or critical care involvement (NICE, 2014: 21-22)
What’s worth bearing in mind during hospital-neuroscience unit transfers of patients with head injuries?
Patients who have a GCS of less than 8 should be intubated
Before transporting, make sure to stabilise the patient and ensure monitoring is attached
A patient ‘with persistent hypotension’ should not be transported until they are ‘stabilised’ (NICE, 2014: 32-33)
During these transfers, patients ‘should be accompanied by a doctor with appropriate training and experience in the transfer of patients with acute brain injury. […] Patients requiring non-emergency transfer should be accompanied by appropriate clinical staff.’
NICE, 2014: 32-33
Reference
National Institute for Health and Care Excellence. (2014). Head injury: assessment and early management (NICE Clinical Guideline 176). Retrieved from https://www.nice.org.uk/guidance/cg176
The first video in the series is Ventilator V2, which was posted some time ago on the website & on YouTube. You may view the original video & more information here.
You may now complete a quiz to test your knowledge instead of or as well as watching the entire video. Each wrong answer will optionally link you to the relevant part of the video.
‘For more than 50 years, treatment strategies have included the use of various drugs, but there is limited evidence that such treatments are effective’ (Perkins et al, 2018).
8014 patients of the 10, 623 initially selected were included in the trial.
Of these, 4015 were given adrenaline and 3999 a placebo.
Of those who were given adrenaline and survived until discharge, 39 (31.0%) out of 126 patients had a ‘severe neurological impairment’ and of those who were given the placebo, the same was true for ’16 of 90 patients [17.8%]’
(Perkins et al, 2018).
Exclusions to the trial
‘…those with anaphylaxis, pregnant women and children’ (below age 16).
After the pilot, life-threatening asthma as a suspected cause of the cardiac arrest was added as an exclusion because of ‘the potential overlap between the presentation of asthma and anaphylaxis’.
Anaphylaxis was excluded because adrenaline is considered potentially ‘beneficial’ for this condition
(Warwick Clinical Trials Unit, 2018).
The trial only looked at the effects of the use of adrenaline during out-of-hospital cardiac arrest and not at the use of adrenaline during ROSC, which is a protocol that some Trusts follow (Warwick Clinical Trials Unit, 2018). In addition, this does not cover any treatment initiated by the hospital if the patient was transported there.
Conclusions
‘the benefits of epinephrine that were identified in our trial are small, since they would result in 1 extra survivor for every 112 patients treated. This number is less than the minimal clinically important difference that has been defined in previous studies.29,30 Among the survivors, almost twice the number in the epinephrine group as in the placebo group had severe neurologic impairment’ (Perkins et al, 2018).
Limitations
Perceived limitations include: ‘Information about the quality of CPR was limited to the first 5 minutes of cardiac arrest and involved fewer than 5% of the enrolled patients.’ (Perkins et al, 2018)
Further limitations to consider could be:
time to CPR
patient’s co-morbitities that weren’t already considered in the study
More information
Warwick’s Clinical Trials Unit have produced an infographic with more information here.
View the University of Warwick’s press release here.
References
NIHR, 2018. Investigating the role of adrenaline in cardiac arrest. Available Online: https://www.nihr.ac.uk/news/investigating-the-role-of-adrenaline-in-cardiac-arrest/8931 (Accessed 19/07/18)
Perkins, G.D. et al, 2018. A randomized trial of epinephrine in out-of-hospital cardiac arrest. New England Journal of Medicine. doi: 10.1056/NEJMoa1806842
Warwick Clinical Trials Unit, 2018. Available Online: https://warwick.ac.uk/fac/med/research/ctu/trials/critical/paramedic2/faqs/ (Accessed 19/07/18)
In a 2010 study of nursing care in an Italian hospital, researchers found that just ‘40% of nursing activities observed were included in the nursing records’ (Marinis et al, 2010). Although this study was about nurses, not prehospital medics, it indicates the potential for missing key information in our documentation. A variety of models exist to help ensure that all the useful information is in your paperwork by the time it’s finalised & to ensure that it’s clear and concise…
Before the methods are introduced, make sure to note the following:
There is not just one method
Patient report forms vary across Trusts. Essential (required) criteria varies too.
Policies regarding paperwork can be found publicly on most Trust websites and will be linked to from here if permission is gained.
There is little freely available information regarding paramedic PCR completion in the UK. Each Trust has their own policy but those policies mainly centre around mandatory fields, not around how to structure your paperwork.
Regardless of what you use, Gregory and Mursell’s (2010: 190) recommendations include ensuring it is ‘clear, accurate and legible [,] […] objective [and] […] first hand’. However, if your information is not first hand, they advise adding the ‘name and position’ of the person who gave you the information (2010: 190).
What do I do if I make a mistake in my paperwork? (link coming soon)
There are 8 models of documentation for medical professionals
A few variations of these may exist where people have chosen to add a letter to the above acronyms to extend the models.
Doctors and websites regularly used by paramedics including Geeky Medics, seem to suggest a combination of the ABCDE, ROS & SOAP approaches, depending on the patient’s presentation (Geeky Medics, 2018).
Simply, this involves transferring information from the DR ABCDE primary survey (Resuscitation Council, 2018) onto paper. Farrington (2018) mentions documenting this approach.
The review of systems (RoS) approach is widely used and accepted in healthcare, and easily assimilates into paramedic practice. RoS improves patient care by holistically assessing the patient, and can make the inter-professional handover of a patient to another team more professionally acceptable. Documentation using the RoS is more comprehensive and less prone to errors. (Jenkins, 2013)
ROS is:
Also known as the systematic enquiry (Douglas et al, 2013: 35)
Recommended by Pilbery and Lethbridge (2010: 191) and forms the structure of the secondary surveys featured in Blaber and Harris (2011).
Part of many models of documentation & not strictly a model on its own
Involves writing a list of systems i.e. Respiratory, Cardiovascular, Central nervous, and listing examinations beneath each subsection. So, for a patient complaining of chest pain the ROS might show:
Cardiovascular
Weak radial pulse
Tachycardic: 95.
No added heart sounds
Pitting oedema
Respiratory
Equal chest movement. No deformities to chest
Bilateral crackles on auscultation
…and so on
(The Regents of the University of California, 2015; Snadden et al, 2013)
*Note these are just examples and are not intended to demonstrate a complete patient report form.
You do not have to review every system for every patient but you should review the ones that are ‘related’ to the presenting complaint or the primary affected system (Blaber and Harris, 2011: 22).
Below is one suggested way to use ROS as part of a complete patient record form:
Presenting complaint – PC
History of Presenting Complaint – HPC
Past Medical History – PMH
Drug History – DH
Allergies
Family History – FH
Social History – SH
On Examination (O/E)
Review of Systems – ROS
Impression – IMP
Plan
(Gregory & Mursell, 2010: 191; Douglas et al, 2013: 32-39)
Variations of this model
The Douglas et al (2013: 32-39) model includes allergies in the drug history section, names review of systems as ‘systematic enquiry’, and includes the on examination section within that enquiry, rather than before it. They also add ‘information given’ to the patient and their relatives, and ‘progress notes’ to the model (Douglas et al, 2013: 39) to separate patient progress from the initial presentation & impression.
However, their model is not designed specifically for prehospital medics. Their example suggests the progress section should be used by Doctors who review patients at a later date. Gregory & Mursell’s (2010: 191) adaptation of this model is designed with Paramedics in mind. Still, a progress note section could be useful for prehospital documentation in situations where the patient’s condition changes in the relatively short time we spend with them. Following a structure which specifies documenting patient improvement or deterioration could help make our documentation clear. Comments? Add them below —>
Note, as mentioned above, that the ROS approach is part of a multitude of different approaches to writing paperwork. It is included in many of the following models either in documenting a patient’s past medical history (Beebe & Myers, 2010: 343-344) or in the secondary survey (Blaber and Harris, 2011), or both.
Including ‘OPQRST (onset, provocation, quality of pain, radiation, severity, timing’ (Beebe & Myers, 2010: 342) where relevant
Including past medical history,
Including review of systems,
Including pertinent negatives.
Note that Beebe & Myers (2010) recommend using the review of systems structure in order to collect information about the patient’s past medical history. Other sources, including Douglas et al (2013) use the systematic enquiry/review of systems as part of the examination section.
Beebe & Myers (2010) include information in the history section of the CHEATED model that is more relevant for insurance-based healthcare systems. Only information relevant to UK medics has been included in this post.
Examination of physical signs
Assessment
Including the patient’s consent & any refusal of care
Treatment
Evaluation
‘Following every treatment there should be an evaluation of the effectiveness of that treatment, or, at a minimum, a statement about the patient’s ongoing condition’ (Beebe & Myers, 2010: 346)
If the patient refuses care of transport, an ‘explanation of outcomes’ can be used here (Beebe & Myers, 2010: 346).
Disposition
This is a summary of the patient & their treatment at the time of handover
Worsening advice if the patient has been left at home
‘For the past 50 years, one of the primary organizing structures for physicians’ clinical documentation have been the SOAP note (Subjective, Objective, Assessment, Plan). The cognitive check list is well-suited to differential diagnosis but may not support detection of changes in systems and/or learning from cases.’ (Lenert, 2016)
There are several other variations of SOAP, including SNOCAMP, which adds the ‘nature of the presenting complaint, counseling, and medical decision making’ (Larimore & Jordan, 1995).
Lenert (2016) have concerns about the subjective section of the SOAP model & the potential for poor decision making due to its structure. Introducing OODA…
Orient, including Predictions = contextualising observations, including consideration of the patient’s wishes and/or needs, prioritising, considering guidelines, consider consequences & develop plans
Decide
Act, including Predictions = treatment & considerations of outcomes
‘there are cognitive models that outline steps that can help novices and experienced users maintain situational awareness and learn in rapidly changing environments. One such model, which was initially developed by Boyd to help Air Force pilots outthink their opponents in aerial combat but is now widely applied within the U.S. military, is the Observe Orient Decide Act (OODA) model.’ (Lenert, 2016)
OODA is:
Designed to be ‘a repeating loop’ (Lenert, 2016)
‘action-oriented’ (Lenert, 2016)
‘allows […] reconsideration of assumptions’ (Lenert, 2016). Put simply, it reminds us to check and re-check
recommended in the ‘subsequent management of patients’ where SOAP is useful in the initial approach to a patient (Lenert, 2016)
‘The goal of the OODA Loop is “think” and “act” faster and better than the enemy [.] […] Bad outcomes occur when medical treatments are not adjusted fast enough, based on current hypotheses about what the illness is, to outpace progression of the illness.’ (Lenert, 2016)
It may help with ‘situational awareness, and in detecting change and errors in diagnosis.’ It may also ‘improve communications by explicitly documenting a clinician’s reasoning and decisions, much of which is not transparent in SOAP notes.’ (Lenert, 2016)
However, it’s worth bearing in mind that neither SOAP nor OODA was originally designed for pre-hospital care.
Could OODA be used as part of a reflective framework? The model focuses on decision making and the key parts of patient assessment, which could become a reflective aid.
Could OODA be used for time-critical patients?
Could OODA be used as part of other models for when patients or situations become challenging or time-critical?
E.g. a patient whose initial presentation is hypoglycaemia, who requires quick decision making but may then become stable
e.g. a patient in an initially safe environment which later becomes unsafe & requires a new plan (for example, abusive or violent patients, relatives or bystanders, or environmental dangers)
In these cases, OODA could be used to document & assist with decision making during parts of jobs.
CHEATED, CHARTIE, OODA and Douglas et al’s (2013: 39) version which includes ROS all have some sort of evaluation featured as part of their models. A useful addition?
Gregory, P. & Mursell, I. 2010. Manual of Clinical Paramedic Procedures, Oxford: Blackwell Publishing
Jenkins, S. 2013. History taking, assessment and documentation for paramedics. Journal of Paramedic Practice, 5 (6): 310-316
Larimore, W.L. & Jordan, E.V. 1995. SOAP to SNOCAMP: Improving the medical record format, The journal of family practice, 41 (4): 393-398
Lenert, L.A. 2016. Toward Medical Documentation That Enhances Situational Awareness Learning, AMIA Annual Symposium Proceedings Archive, 2016: 763-771
Marinis, D. et al (2010) ‘If it is not recorded, it has not been done!’? consistency between nursing records and observed nursing care in an Italian hospital. 19. (11-12). 1544-52. doi: 10.1111/j.1365-2702.2009.03012.x
Pilbery, R. & Lethbridge, K. 2016. Ambulance Care Practice, Bridgwater: Class Professional Publishing
This post is yet to be peer reviewed. Human error may still exist in the reference list or in the body of the article. Please get in touch if you have any comments.
Harris, 2016; Pilbery & Lethbridge, 2016 *This can be made available in alternative formats & colours on request*
And more…
Harris, 2016; Pilbery & Lethbridge, 2016 *This can be made available in alternative formats & colours on request
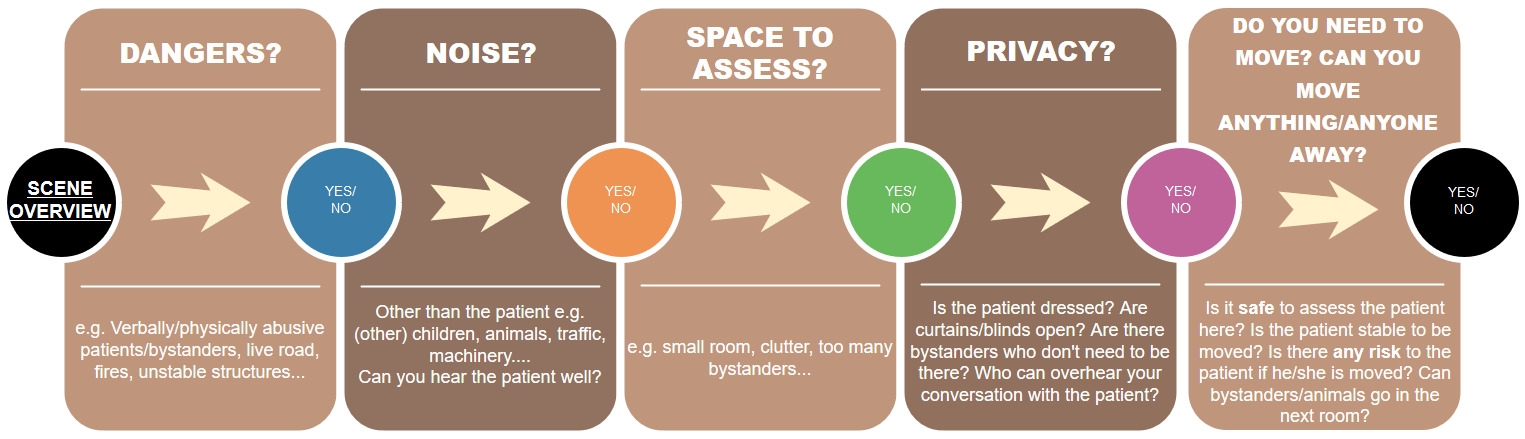
You may find varying suggestions for what to consider in what is usually referred to as your ‘scene assessment’ (Harris, 2016: 1; Pilbery & Lethbridge, 2016: 126) or ‘end of bed […] assessment’ (Spurr, 2014). This is a cheat sheet to assist you in identifying these important factors. There are a few examples within each category, forming part of what is surely an endless list. Harris (2016: 1-3) also recommends considering use of PPE, considering vehicle position, and considering CBRNE incidents. Pilbery & Lethbridge (2016: 127) recommend considering outside/inside temperature, terrain that is not reachable by land ambulance, and referring to major incident guides where applicable. Major incidents are not covered within this cheat sheet, but this sheet may guide you through the initial thought process prior to announcing a major incident…
Final Note & References
This is a cheat sheet which is designed to complement your scene assessment. This cheat sheet is in the author’s own words but ideas have been used from the below texts. Any copies of the above cheat sheets should be paired with the below references.
Harris, G. 2016. ‘General principles of assessment’ in A.Y. Blaber and G. Harris, ed. 2016. Assessment Skills for Paramedics, 2nd ed. Berkshire: Open University Press, pp. 1-13
Pilbery, R. and Lethbridge, K. 2016. Ambulance Care Practice, Bridgwater: Class Professional Publishing
Spurr, J. 2014. End-of-Bedogram: The Art Formally Known as Intuition, Available Online: http://injectableorange.com/2014/03/end-bedogram-art-formally-known-intuition/ (Accessed 26/03/18)
Feedback? Comments? Please post below…
This post is yet to be peer reviewed. Please get in touch if you have any comments.
So far, Article 999 has a reasonable collection of information and videos about positive pressure breathing and ventilators used in prehospital emergency care. Smiths Medical is behind the PneuPac ParaPac. They have kindly given their permission to share the following documents, which are available for those who want to read more, find out about other available ventilators, or find an answer not available here.
A shorter version of Ventilators: Why, What, How, When? featuring how-to use the ventilator demonstrations only. Made by UK Paramedics, this demonstrates how to use the PneuPac ParaPac ventilator.
You must read the full disclaimer at www.article999.co.uk/about/ (disclaimer tab) before putting into place anything you see here. Useful information is available in the text on this video, so if you only listen to the narration you will miss important facts. The ventilation settings mentioned in this video are what is recommended by Smiths Medical, current guidelines and some articles – however, as with all topics, there is always varying information available online & alternative expert advice, and no video can cater for all of that. Similarly, this video is intended to demonstrate how to use equipment & to introduce or remind you to the Why, What and When of ventilators – not to tell you that you should or shouldn’t be using it. That is dependent on local guidelines, your research & your choice as a clinician. This video merely highlights the varying advice regarding tidal volume settings, and in the text points out the potential problems with some of the figures. No specific volume is recommended.
Transcript
Article 999. Ventilators: Why, What, How, When?
This video has been made by UK Paramedics following guidelines. It is not endorsed by any author, organisation or Ambulance Trust. You must read the full disclaimer at www.article999.co.uk/about/ and refer to your local guidelines before putting into place anything you see here. This video is intended to demonstrate how to use the ventilator according to use guides and guidelines – not to tell you that you should or shouldn’t use it. That decision is up to you and should be dependent on local guidelines and your own research. This is what the textbooks, the manufacturer and a few articles say & is not intended to represent the expert opinions or experience of others within healthcare.
Remember hand hygiene, bare below the elbows and gloves in real life.
How?
To remove the ventilator from the racks, pull the flap to the side and push the ventilator up. To put it back in, simply push it down and pull the flap to the side again.
To connect to the gas supply, push the hose into the socket and twist. It’s the same when connecting to a portable oxygen cylinder.
When you turn it on, the ventilator should complete a self check. The alarm lights should flash in sequence, there should be one burst of the high pressure audible alarm, and the orange indicator should flash for 60 seconds.
Next, check the indicator shows white for O2.
Connect the patient circuit [shown in video].
Next on the list, adjust the ventilation parameters. Set the air mix control to no air mix for respiratory arrest or CPR. Set the relief pressure control to 40. Set the respiratory rate to 12. As for the tidal volume, it varies massively as you can see on the screen. It depends on whether you opt for an average value or base it on the patient’s weight. Smiths Medical (2017) advise 800-900ml on their training video, [but this may not be advisable] but don’t worry too much about the slight differences in tidal volume because the PneuPac features a high pressure alarm that we’ll discuss shortly. The alarm will help you identify if the tidal volume is too high for your patient.
The middle one tells you when breathing is detected by the ventilator
(Smiths Medical, 2017)
High pressure = excessive tidal volume, incorrect airway position, kinked ET tube, or incorrect ventilation settings.
If the pressure is reaching it’s max, there may be something wrong with the circuit.
If you’ve checked the above and the alarm is still sounding, Smiths Medical (2017) advise that your tidal volume setting might simply be too high.
Low pressure = leakage or insufficient tidal volume/settings, faulty valve in the patient’s circuit
This alarm tends to occur when pressure drops below 10cmh20
Earlier, I pointed out the alarm in the middle, at the bottom. This is SMMV. It’s an indicator that will flash green if the patient is breathing for themselves. The ventilator will assist if the patient breathes with less than 150ml of tidal volume. Between 150-400ml the ventilator will extent the exhalation time to allow the patient to complete their own breath, and above 400ml the ventilator will allow the patient to breathe and will not assist, but may still assist on the next breath if required (Smiths Medical, 2017; Baker, 2012).
Extra facts:
McCarty et al (2012) found that ‘ventilation rates and tidal volumes commonly exceeded Guideline recommendations. This resulted in […] excessive mean airway pressure’
Smiths Medical (2017) advise that peak inflation pressure should be below 20cmh20 when using a mask to ventilate due to the issues of too high pressure
Inspiration to Expiration should be 1:2 (Smiths Medical, 2017; Baker, 2012)
References
Baker, D. 2012. Emergency and Transport Ventilation, an introductory guide, Smiths Medical International Limited: Luton
You must read the full disclaimer at www.article999.co.uk/about/ (disclaimer tab) before putting into place anything you see here. Useful information is available in the text on this video, so if you only listen to the narration you will miss important facts. The ventilation settings mentioned in this video are what is recommended by Smiths Medical, current guidelines and some articles – however, as with all topics, there is always varying information available online & alternative expert advice, and no video can cater for all of that. Similarly, this video is intended to demonstrate how to use equipment & to introduce or remind you to the Why, What and When of ventilators – not to tell you that you should or shouldn’t be using it. That is dependent on local guidelines, your research & your choice as a clinician. This video merely highlights the varying advice regarding tidal volume settings, and in the text points out the potential problems with some of the figures. No specific volume is recommended.
Transcript
Article 999. Ventilators: Why, What, How, When?
This video has been made by UK Paramedics following guidelines. It is not endorsed by any author, organisation or Ambulance Trust. You must read the full disclaimer at www.article999.co.uk/about/ and refer to your local guidelines before putting into place anything you see here. This video is intended to demonstrate how to use the ventilator according to use guides and guidelines – not to tell you that you should or shouldn’t use it. That decision is up to you and should be dependent on local guidelines and your own research. This is what the textbooks, the manufacturer and a few articles say & is not intended to represent the expert opinions or experience of others within healthcare.
Remember hand hygiene, bare below the elbows and gloves in real life.
Why use the ventilator?
Research suggests that mechanical ventilators can reduce the variability of breath timings & as a result, capnography readings. They can also increase the likelihood of ‘effective ventilation’ (Owen and Castle, 2006)
To quote from Gregory & Mursell (2010: 47) ‘A high flow rate over a short inflation time inevitably produces a high peak airway pressure in an unprotected airway [as with BVM technique]. High peak airway pressure overcomes the pressure of the lower oesophageal sphincter and causes gastric inflation. […] Use of […] mechanical ventilation may help to overcome the high pressures involved. […] In an intubated patient or a patient with an LMA in situ, use of a mechanical ventilator has been shown to allow paramedics to accomplish extra tasks, document better, and provide better patient care’ (Gregory & Mursell, 2010: 47)
What?
This is a time-cycled, volume preset flow generator (Baker, 2012). In other words, the pressure can vary, volume is always the same, and the air must be delivered within a preset time, which helps to control the tidal volume.
There are many different types. One of the most common ones in UK ambulances at this time (Gregory & Mursell, 2010: 44) is the Pneupac paraPAC (Smiths Medical, 2017) but the ParaPac Plus may soon replace it.
Here are the useful parts:
The supply gas failure alarm
The inlet connection
The relief pressure control
The ‘main pneumatic switch’
Air mix control
Inflation pressure monitor
Frequency control
Tidal volume control
(Pilbery and Lethbridge, 2016: 189)
How?
To remove the ventilator from the racks, pull the flap to the side and push the ventilator up. To put it back in, simply push it down and pull the flap to the side again.
To connect to the gas supply, push the hose into the socket and twist. It’s the same when connecting to a portable oxygen cylinder.
When you turn it on, the ventilator should complete a self check. The alarm lights should flash in sequence, there should be one burst of the high pressure audible alarm, and the orange indicator should flash for 60 seconds.
Next, check the indicator shows white for O2.
Connect the patient circuit [shown in video].
Next on the list, adjust the ventilation parameters. Set the air mix control to no air mix for respiratory arrest or CPR. Set the relief pressure control to 40. Set the respiratory rate to 12. As for the tidal volume, it varies massively as you can see on the screen. It depends on whether you opt for an average value or base it on the patient’s weight. Smiths Medical (2017) advise 800-900ml on their training video, [but this may not be advisable] but don’t worry too much about the slight differences in tidal volume because the PneuPac features a high pressure alarm that we’ll discuss shortly. The alarm will help you identify if the tidal volume is too high for your patient.
The middle one tells you when breathing is detected by the ventilator
(Smiths Medical, 2017)
High pressure = excessive tidal volume, incorrect airway position, kinked ET tube, or incorrect ventilation settings.
If the pressure is reaching it’s max, there may be something wrong with the circuit.
If you’ve checked the above and the alarm is still sounding, Smiths Medical (2017) advise that your tidal volume setting might simply be too high.
Low pressure = leakage or insufficient tidal volume/settings, faulty valve in the patient’s circuit
This alarm tends to occur when pressure drops below 10cmh20
Earlier, I pointed out the alarm in the middle, at the bottom. This is SMMV. It’s an indicator that will flash green if the patient is breathing for themselves. The ventilator will assist if the patient breathes with less than 150ml of tidal volume. Between 150-400ml the ventilator will extent the exhalation time to allow the patient to complete their own breath, and above 400ml the ventilator will allow the patient to breathe and will not assist, but may still assist on the next breath if required (Smiths Medical, 2017; Baker, 2012).
When?
– AACE (2016) recommend considering ventilation if a ptn’s o2 sats <90 on high con o2,
if the RR is <10 or >30 bpm or if there is ‘inadequate chest expansion’ (p42) but the mechanical ventilator is to be used …
– for ’emergency and transport ventilation’ in 5kg + patients (Smiths Medical, 2017)
Extra facts:
McCarty et al (2012) found that ‘ventilation rates and tidal volumes commonly exceeded Guideline recommendations. This resulted in […] excessive mean airway pressure’
Smiths Medical (2017) advise that peak inflation pressure should be below 20cmh20 when using a mask to ventilate due to the issues of too high pressure
Inspiration to Expiration should be 1:2 (Smiths Medical, 2017; Baker, 2012)
References
Baker, D. 2012. Emergency and Transport Ventilation, an introductory guide, Smiths Medical International Limited: Luton