This is a discussion I have had with several people recently. I’ve observed the same discussion on social media: Is it better to specialise by taking specific job roles or courses, or to keep up with the ‘jack of all trades’ role of a Paramedic?
Our profession is at a point of developing specialisms that seem to be staying put. We can now work in primary and urgent care, in research, in palliative care, resuscitation and education roles, or in other community roles such as rapid response. There are ACCP routes popping up around the country. There are resuscitation roles in specialist hospitals, and community roles that focus expertise on specific conditions. I can see a potential future for new staff being one of a few years of general practice, followed by a series of options containing different specialities and of course, different rotas. This is the way other professions have gone and of course, Paramedicine is young compared to the role of a Doctor or Nurse. Perhaps it is only natural for career paths like these to develop over time. It certainly makes for a more interesting, unique career, and it allows us to develop expertise. Specialising also contributes to a clear CV that should help lead to further roles in the area. It could be argued that without emphasising those areas of expertise on our CV, we might stand out less to a potential employer.
Some argue that remaining general means we never develop expertise in any given area, hence the ‘jack of all trades’ expression that I have heard previously expressed about our profession – we all know how that expression ends. Can anyone be a master of all?
Many of the roles currently available offer part-time work. I am working in one of these, four days a week. It means the majority of my time is spent with adults, but as I maintain frontline shifts I could still come across paediatrics and maternity jobs. I may specialise in one or two areas, but if this means I do not develop in other areas then I am not being honest with myself: I need more CPD related to those areas I now come across less because I am at risk of deskilling. If I want to develop as a Paramedic then surely I need to develop in all areas of practice.
My answer to this conundrum is simple: If you do not intend to maintain any frontline work, you do not need to remain general. But if you intend to keep up any of that work, even if this will only be occasional, you must develop in all areas within your remit. You may still specialise and opt for higher level courses in the areas that take up the majority of your time, but it seems sensible to ensure you develop in all the areas you work in. It’s those areas we see the least that will make us the most hesitant. I cannot safely leave my paediatric knowledge behind with what I learned several years ago when I could still see young patients. I cannot stop learning about maternity when those jobs have the potential to be so time-critical. I don’t want to stop focusing on trauma.
I believe to be the best for our patients, we must juggle all areas. Our expertise is then not necessarily about the courses we have done but the experience we have gained. As I spend the majority of my time working in one or two areas, I could argue those are my specialisms – but I am also still remaining general.
There are so many different recommendations of ECG Interpretation. Some books have 5 steps, some 6, some 9, some 11. Below, I have listed a few common ones in the hope of highlighting the differences – and the similarities. I have tried to focus on rhythm strip analysis only but some methods combine the rhythm strip with the 12 lead analysis. I have only included those that are publicly available, so although some fantastic methods are taught on courses, I can’t reference them and have subsequently omitted them. However, if you have a preference or believe one method should be included below, add it in the comments and it may be featured in a future update.
Method one:
From: Resuscitation Council, Advanced Life Support (2021: 106):
The 6 Steps of rhythm strip analysis:
1. Is there any electrical activity? (Or/and check a pulse)
2. What is the ventricular (QRS) rate?
3. Is the QRS rhythm regular or irregular?
4. Is the QRS complex width normal (‘narrow’) or broad?
— 5. Is atrial activity present?
6. Is atrial activity related to ventricular activity and, if so, how?
Method Two:
From: Charles L. Till, Clinical ECGs in Paramedic Practice (2021: 16):
9 Steps – initially look at lead II, then look at every ECG lead:
ECG Steps 1. What is the rate and rhythm? 2. Are there any P waves and what is their relationship with the QRS complex? 3. What is the duration and morphology of the QRS complex?
4. Is the ST segment isoelectric, depressed or elevated? 5. Are the QT intervals and T waves normal?
Clinical Steps 6. Is the heart generating a palpable pulse of appropriate rate and providing adequate perfusion? 7. Is the rhythm unstable and at risk of deterioration? 8. Does the presenting rhythm support or change your working diagnosis? 9. Are any clinical interventions required?
Method Three:
From: Paul Murray, East of England Ambulance Service, Version 1.0, ECG Recognition – Quick Reference Guide (Feb 2014: 1)
6 steps:
1. ‘QRS Rate’
2. ‘Is the QRS rhythm regular or irregular?’ (and regularly irregular or irregularly irregular?)
3. ‘QRS duration’
4. ‘Are P waves present?’
5. ‘Relationship between P waves and QRS – is there a P wave for each QRS and a QRS for each P wave?’
6. ‘Is the PR interval within normal limits 120-200ms and is it constant?’
(This is basically the same as the RC council method, with one added step; the RC method has one step at the start – a reminder to ensure the leads are connected properly and the patient is alive).
Method Four
From: Fred Kusumoto & Pam Bernath, ECG Interpretation for Everyone – An On-The-Spot Guide (2012: 33-36):
‘Assess the patient: symptoms and physical examination. Appearance, vital signs, physical examination’ -> 1. Is there a P wave in front of every QRS and is the rate between 50-100 beats per minute? 2. Are the ST segments isoelectric?
Each answer leads you to a different figure – an option to confirm you have a normal ECG, evaluation of ST segments, evaluation of arrhythmias, or confirmation time-critical patients.
The normal ECG should have: 1. Rate should be between 50 and 100bpm
2. A P before every QRS (Positive P in lead II).
3. The QRS in V1 should be narrow an negative i.e. an Rs
4. The ST segment should be isoelectric
5. The T wave should be the same direction as the QRS
Method Five:
From: Kuhn, Lang, and Wiesbauer, ECG Mastery: The Simplest Way to Learn the ECG (2014: 141-142)
Summarised – 11 steps (taking you from rhythm analysis into 12 lead analysis. Steps included to highlight how some of the steps above are readdressed or appear later altogether here; other points may appear in front): 1. Rhythm. Criteria for sinus rhythm:
Fast Fact posts are designed to provide quick and easy ways to revise key topics – view a photo with a quote/fact by simply scrolling through the category. Refresh yourself during those middle-of-the-night breaks when you would have aimlessly scrolled through your phone. There is no need to read a lengthy post to do a little CPD. For more fast facts, head here.
Welcome to a brand new resource containing a searchable collection of charities and companies providing support, information, tools, equipment, food banks and more! Categorised by health condition, circumstance or age group and available for all patients in the UK, we hope you can find useful preventative and supportive help when you need it. This is also available for health-care professionals looking for referral tools and CPD.
The information below has been collated by Article 999’s Founder Louise, along with some help from contributors. Within each category are charities or companies that provide services or equipment that can help you. Please see the ‘date added’ to be certain how up-to-date the information is. Please add comments below, like, and share to let us know what you think and if there are any other charities you would like to see listed here.
This information will be added to. Article 999 is currently not endorsed by any of the charities or companies listed below. If you are a charity and would like to see your posters beside your information, or if you would have any queries, please get in touch by emailing article999uk[at]gmail[dot]com.
HCPs, please do share this with your patients and use the information to enhance your referrals. Some entries below include CPD links for you as well as information for your patients.
What to Do If You Fall (Adults Under 65) – When to Call for Help
What to do if you fall (adults under 65) and you are not hurt.
More
Adults under 65 who fall regularly may be interested in watching Article 999’s video about when to let your Doctor know about your falls. This is available on the over-65s page but please don’t be offended – the reasons to let your Doctor know will still be applicable.
[tabby title=”For Patients”]
Transcript
*Full references at end of page
If you have fallen over and you’re not sure what to do, or would like some additional information, please keep watching. If an ambulance crew have seen you and you have not attended hospital, this video is also for you.
If you or the person you are watching this for has just fallen and the following apply, please call 999.
If you or they fall again, and the following applies, please call us back:
SYMPTOMS:
You are having difficulty breathing, or have chest pain
You’re unable to move your arms or legs, or they’re numb
You have sudden, new weaknesses
You are dizzy and feel faint when you stand up
You lost consciousness, or have had a seizure, which is not normal for you.
You can’t remember what happened since, or before, you fell over
You have continuous vomiting, or headaches, which is not normal for you.
Your behaviour is different – you feel more confused, or more irritated
call 999
PAIN –
You have neck or back pain
You are unable to get up from the floor
You have another injury that PREVENTS YOU FROM WALKING or causes EXTREME PAIN, for example, you think you might have broken your leg.
call 999
HOW IT HAPPENED –
You have fallen from height – more than 1m
You have landed on your head
call 999
If you have had alcohol, this may be hiding symptoms, making it more difficult for us to assess you. If you are intoxicated, you may be advised to attend a&e to rule out serious complications that are masked by the alcohol.
If you have been advised to attend a&e and have chosen not to, please make sure you have someone who can check in on you over the next 48 hours (NICE, 2014), and ask them to look out for these symptoms.
Also, if you take any medications to thin your blood, AND you have hit your head, you must attend a&e to be monitored and receive a scan of your head, a CT scan. Even if you have not drawn blood, you are still at risk of bleeding internally, especially in the brain because these medications are designed to prevent blood clots.
These medications might be called:
Warfarin
Rivaroxaban
Dabigatran
Apixaban
Edoxaban
Heparin (injection)
You might also be taking any of these antiplatelet medications:
Clopidogrel, aspirin, and others shown on the screen:
Dipyridamole
Prasugrel
Ticagrelor
Cangrelor
(BNF, n.d.)
*These are more concerning when taken in combination, e.g. clopidogrel + aspirin
You should also attend a&e when taking these, or at minimum maintain extreme caution for the same reason. For more information about blood thinners and antiplatelets, please scroll below the video.
What to do if you are on the floor because of a fall, and you’re not hurt
Don’t get up quickly. Roll onto your knees and use nearby stable furniture to push yourself up. Then, sit down until you feel able to continue with your day (NHS, 2021). If you are disabled, ensure use your mobility aids today to prevent yourself from falling again.
Remember, if you have hurt yourself, or you can’t get up, call for help. If you have one, you can press your personal alarm. You can call: family, friends, 999, or 111. Both 999 and 111 will lead to an ambulance arrival with a crew who can assess you and help you up. Both 999 and 111 result in the same ambulance service.
While you wait, the NHS recommends changing your position ‘at least once every half hour or so,’ (NHS, 2021) if you are able to and it is not painful to do so.
Keep yourself warm and let 999 know if anything gets worse.
PREVENTION –
To prevent yourself falling again, remove any objects that might have caused you to fall, avoid drinking too much alcohol, and ensure you wear appropriate safety equipment when performing sports, such as helmets when cycling.
Alter SM, Mazer BA, Solano JJ, et al. (2020). Antiplatelet therapy is associated with a high rate of intracranial hemorrhage in patients with head injuries. Trauma Surgery & Acute Care Open, 5(1), e000520
NICEd. (2014). Head injury: assessment and early management (NICE Clinical Guideline 176). Available at: https://www.nice.org.uk/guidance/cg176 (Accessed 16/06/2020).
Nishijima, D. (2012). Immediate and delayed traumatic intracranial hemorrhage in patients with head trauma and preinjury warfarin or clopidogrel use. Annals of Emergency Medicine, 59(6), pp: 460-468.
North American Thrombosis Forum. (2020). Falls and anticoagulation. Available at: https://natfonline.org/2020/08/falls-and-anticoagulation. (Accessed 18/10/2021).
Probst, M. et al. (2020). ‘Prevalence of Intracranial Injury in Adult Patients With Blunt Head Trauma With and Without Anticoagulant or Antiplatelet Use’. Annals of Emergency Medicine, 75(3), pp: 354-364.
Soliman, Y., Meyer, R., And Baum, N. (2016). Falls in the Elderly Secondary to Urinary Symptoms. Reviews in Urology. 18(1), pp: 28-32.
Stiell, I. et al. (2003). ‘The Canadian C-Spine Rule versus the NEXUS Low-Risk Criteria in Patients with Trauma’, The New England Journal of Medicine. 349. pp: 2510-2518.
Please feel free to share this video with your patients, but please attach this link with it so that all accompanying information is also shared.
For more info about what Article 999 is, and why I am creating videos for patients, please see the ‘About Us’ page and click on the ‘About article 999 for patients’ tab.
Feel free to add comments or feedback. Please let us know how well received this is.
Thank you,
Louise Sopher HCPC Registered Paramedic Article 999 Founder
Often basic ECG teaching relies on teaching pattern recognition, which can work well, however when presented with an ECG that isn’t similar to a pattern you have seen, you can run in to problems.
This article will explore two simple concepts that will hopefully help with your ECG reading and understanding of the underlying physiology:
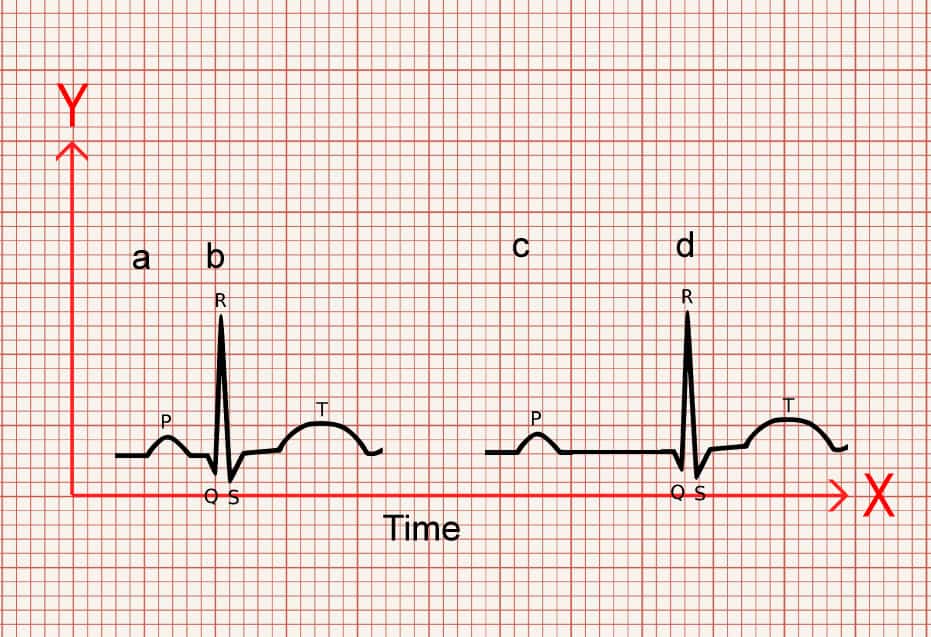
It can be good to think of an ECG as a graph with an X and Y axis. X, horizontally along the bottom represents time. We’ll come to the Y axis later.
Now, we know that X is time, each small square is 40ms (0.04seconds), each large square is 200ms (0.2 seconds), 30 large squares is 6 seconds and so on. That’s reasonably straightforward, but how does it relate to physiology?
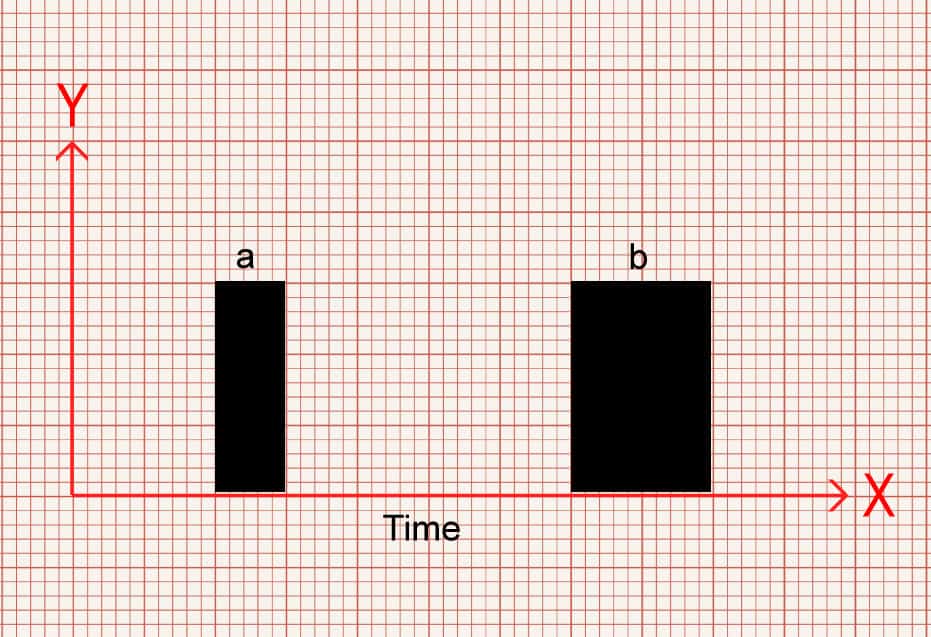
Let’s imagine that graph again. And let’s imagine some boxes drawn on. Don’t worry about the Y axis value for now.
In image 1 you can see a narrow box (a) and a wider box (b). Which one would you say takes up more time? Which one takes up less time?
Box b takes up more of space along the X axis so therefore takes up more time. Box a covers less space on the X axis so takes less time.
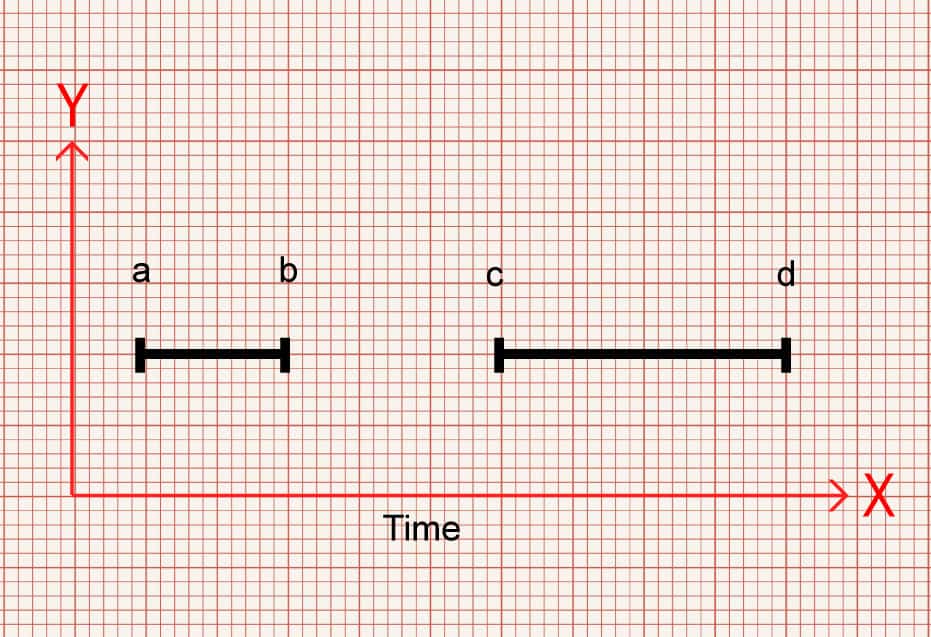
Similarly, we can measure between two points. Look at Image 2. You can see two horizontal lines of different lengths. The gap between a – b is shorter than c -d. So again, which takes up more time?
Gap c-d is wider, takes up more of the X axis and therefore takes up more time.
Stay with me.
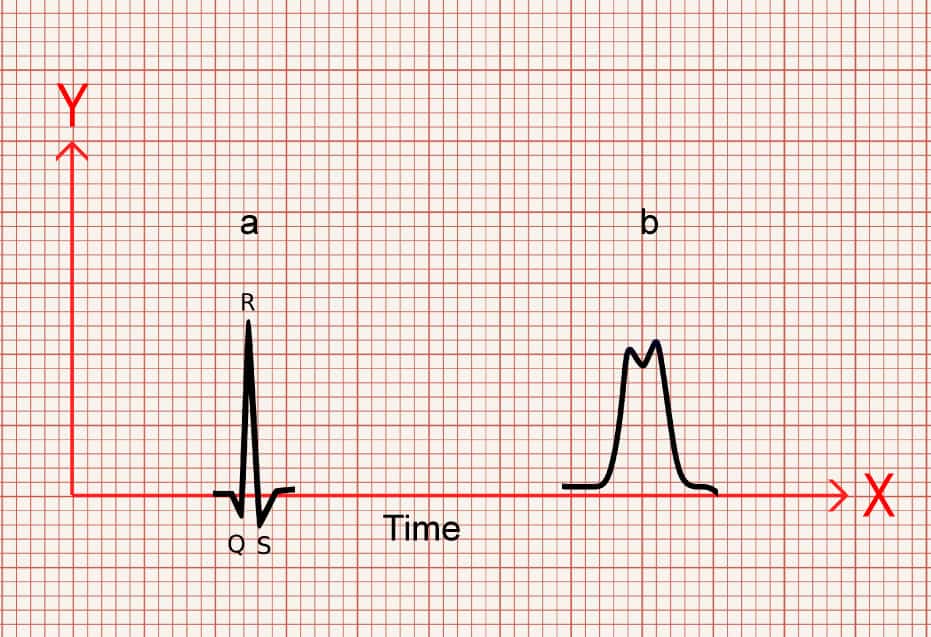
Now, let’s replace those boxes with QRS complexes.
In image 3 there is a narrow QRS (a) and a wider QRS (b). Which one takes up more time?
B is taking up more of the X axis so takes more time.
And again, once more, let’s look at some gaps between two points, but let’s show it as the gap between the P wave and QRS. Which one takes up more time and which takes up less time?
The gap between a-b is shorter than c-d.
So c-d takes up more time.
Probably not ground breaking.
But, what’s another way of thinking about the time something takes? If something takes up more time, you could also say that it is slower, and if something takes up less time, its faster.
Now, remember that an ECG is dealing with electrical conduction.
If on an ECG something is taking up more space along the X axis, therefore taking more time, and is therefore slower, then it makes sense that there is a problem effecting its ability to conduct!
And poor conduction is the underlying issue that what we see in AV blocks and bundle branch blocks.
So if you see a QRS or PR that is wider than normal values, think, something is causing it to be slower and that there is a conduction fault.
Equally if you see a PR interval that is narrower than it is meant to be, taking up less space along the x axis and therefore less time, think, it’s conducting faster than it should and it would alert you to pre-excitation problems, such as accessory pathways in Wolff-Parkinson-White syndrome (WPW effects both the PR interval making it shorter, and has a wider QRS).
Direction
Now, let’s talk about direction.
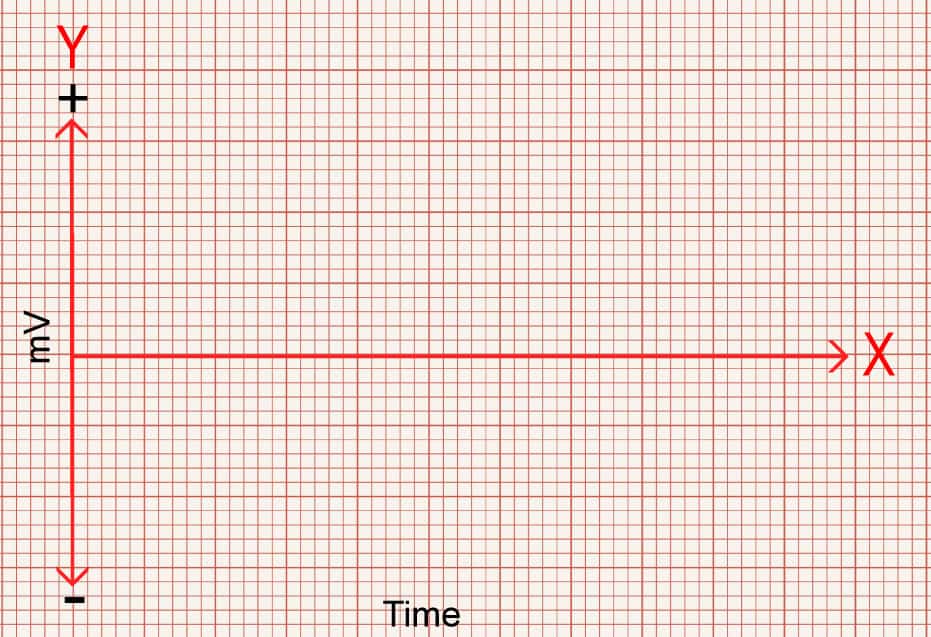
We know by looking at the ECG paper that vertically, the small boxes, measured in mm, represent millivolts (mV) – a measure of force (sort of). Each 1mm = 0.1mV, 10mm = 1mV. This also means that it has what’s known as magnitude – or size.
Now, let’s look at the graph again. We know the X axis is time, as discussed above. However, in an ECG the X axis is not simply the bottom, but instead the middle of the graph, with the Y axis extending both positively above the X, and negatively below the X axis.
The X axis can have readings above or below it. This is the isoelectric line.
ECGs pick up electrical charge moving across the heart. And it does so by placing electrodes at different locations around the heart.
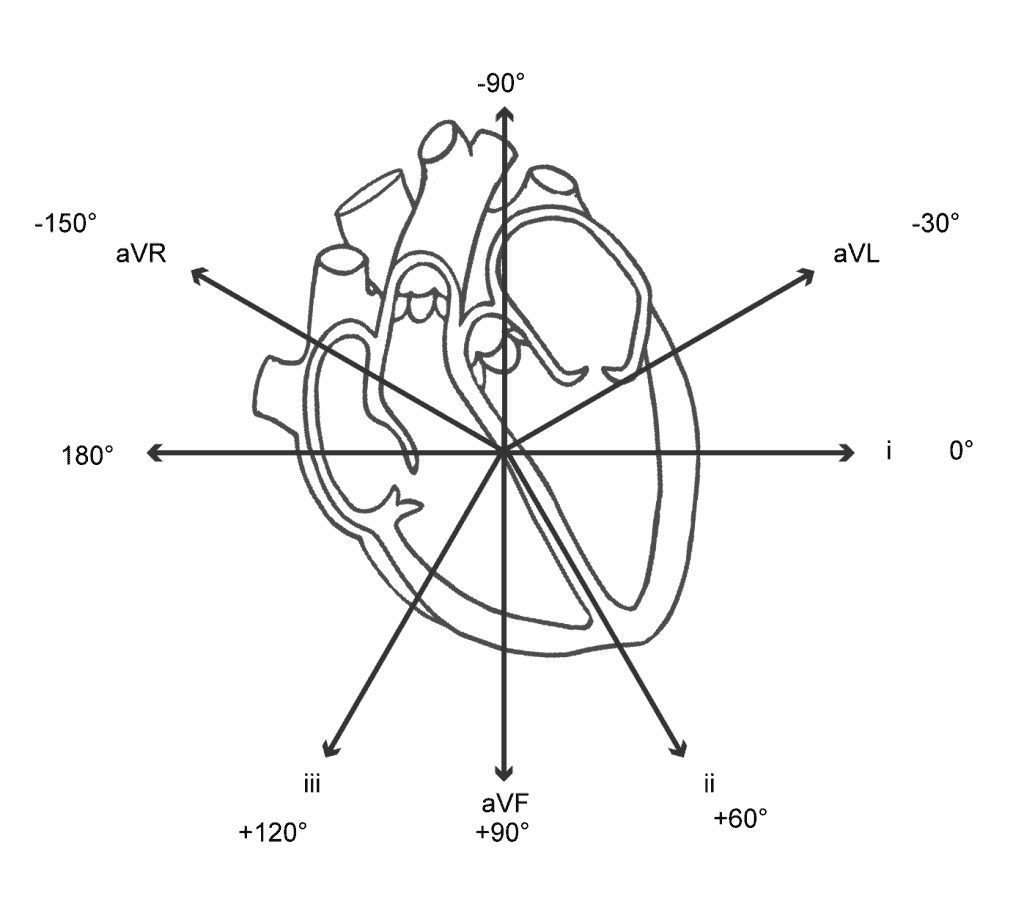
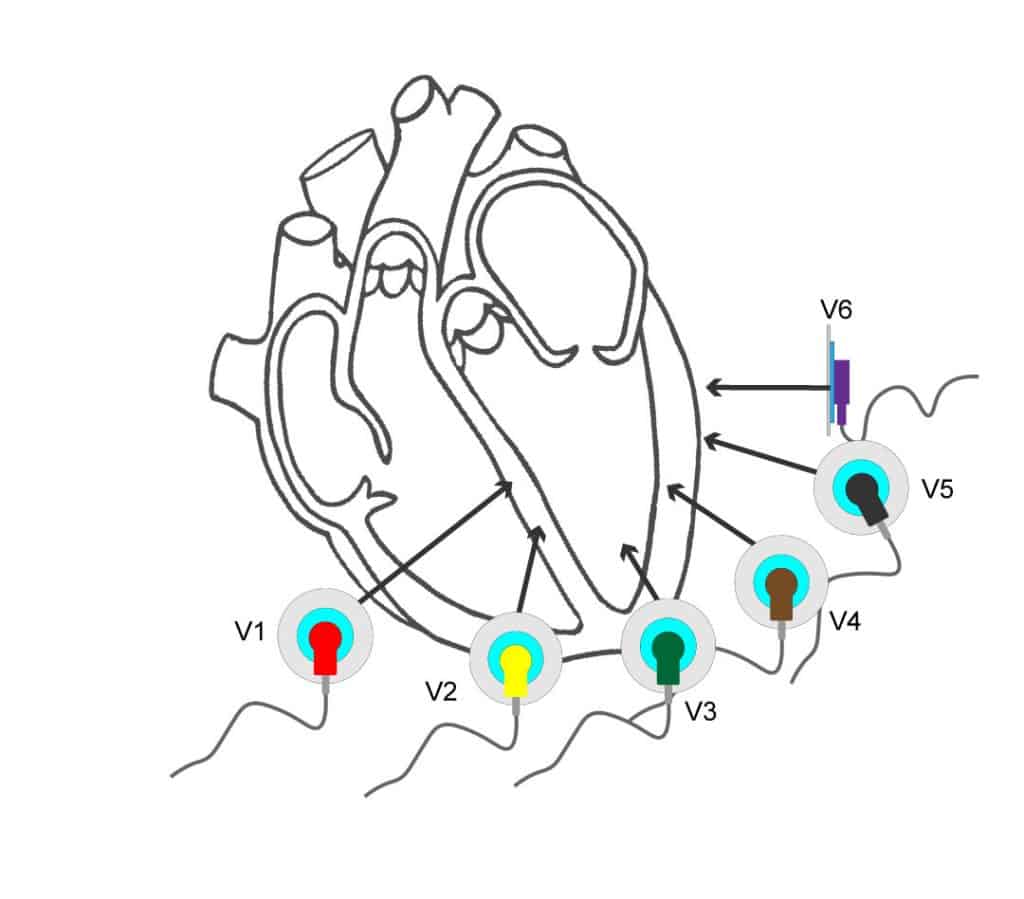
As shown in the diagram below, the electrodes create a view of the heart from different angles, and each view is called a lead. 12 leads (views), but only 10 wires.
The chest leads look at the heart across the transverse plane, that is from the front of the chest to the back, whereas the limb leads look at the heart in the frontal plane, which are essentially from the sides, top and bottom.
The angles the leads look at the heart are measured in degrees, with lead i being the reference point of 0°.
This is something that is worth learning so that you are able to visualise where each lead “looks”.
Roughly speaking, the limbs leads create the following views of the heart.
avR – Looks from the Right shoulder to the left hip
aVL – Looks from Left shoulder to right hip
i – Looks from the left mid axilla similar to V6
ii – Looks from the left hip to right shoulder
aVF – Looks from the Feet up to the head
iii – Looks from the right hip to the left shoulder
The chest leads create views from the chest wall through to the back
V1 + V2 – intraventricular septum
V3 – V4 – anterior wall of the left ventricle
V5 – V6 – lateral wall of the left ventricle
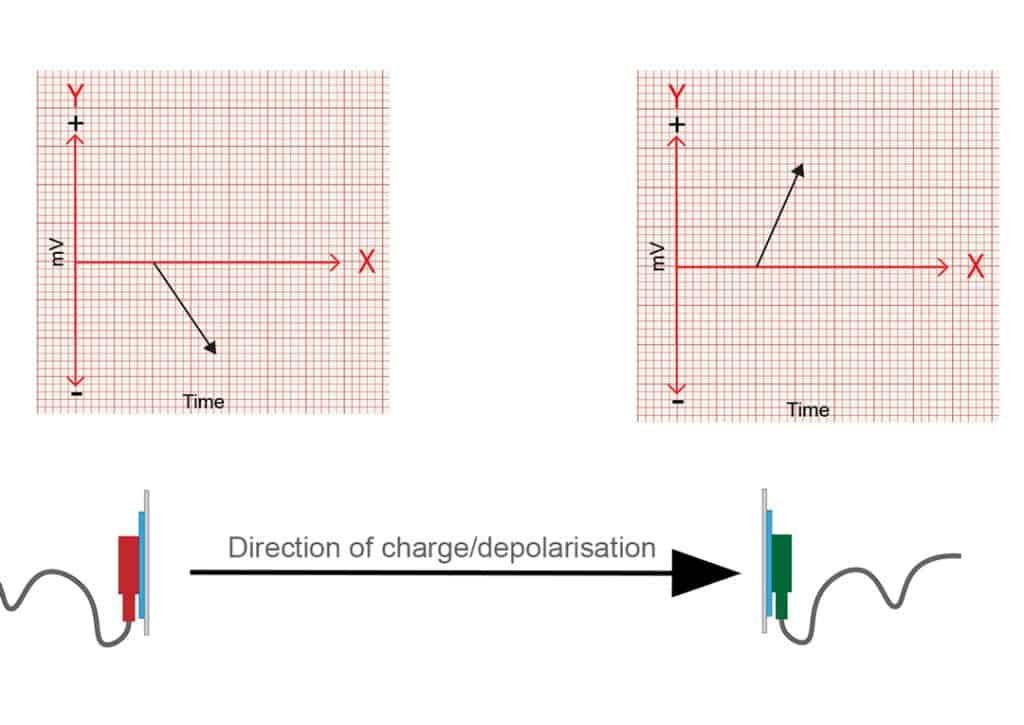
Very simply put, as an electrical charge moves towards an electrode position, this creates a positive reading. As it moves away it creates a negative reading.
Electrodes that are opposite to each other, 180 degrees apart, will be mirrored. One will have charge moving towards it, creating a positive deflection and the opposite side will show a negative deflection as the charge moves away from it.
Leads at 180° from each other.
Slightly more complicated is what happens when the electrical charge isn’t moving directly to, or away from the electrode, but when it is moving at more or less than 180 degrees to the electrodes position.
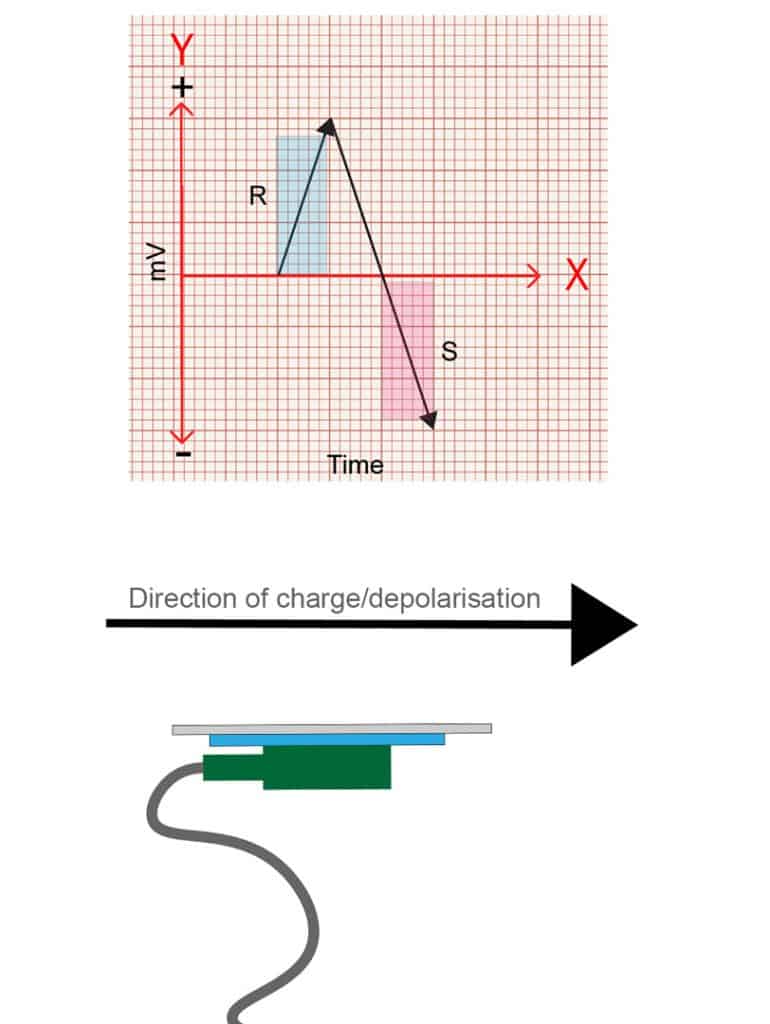
Let’s look at what happens when it moves at 90 degrees to the electrode first.
When the charge is moving at 90 degrees, or perpendicular, to the position of the electrode, it has both a period of positivity and a period of negativity, as the charge moves towards and then away from the electrodes position as it passes by. This is represented on an ECG as an R wave followed by an S wave of equal magnitude.
Quick tip – an R wave is any positive deflection you see, and an S wave is a negative deflection following an R wave BUT it must cross the isoelectric line to be considered negative. The segment from the top of the R wave back to the isoelectric line is not the S wave. The S wave is only the portion below the isoelectric line.
Hopefully this is starting show the relationship between the direction of the charge and the position of the electrode.
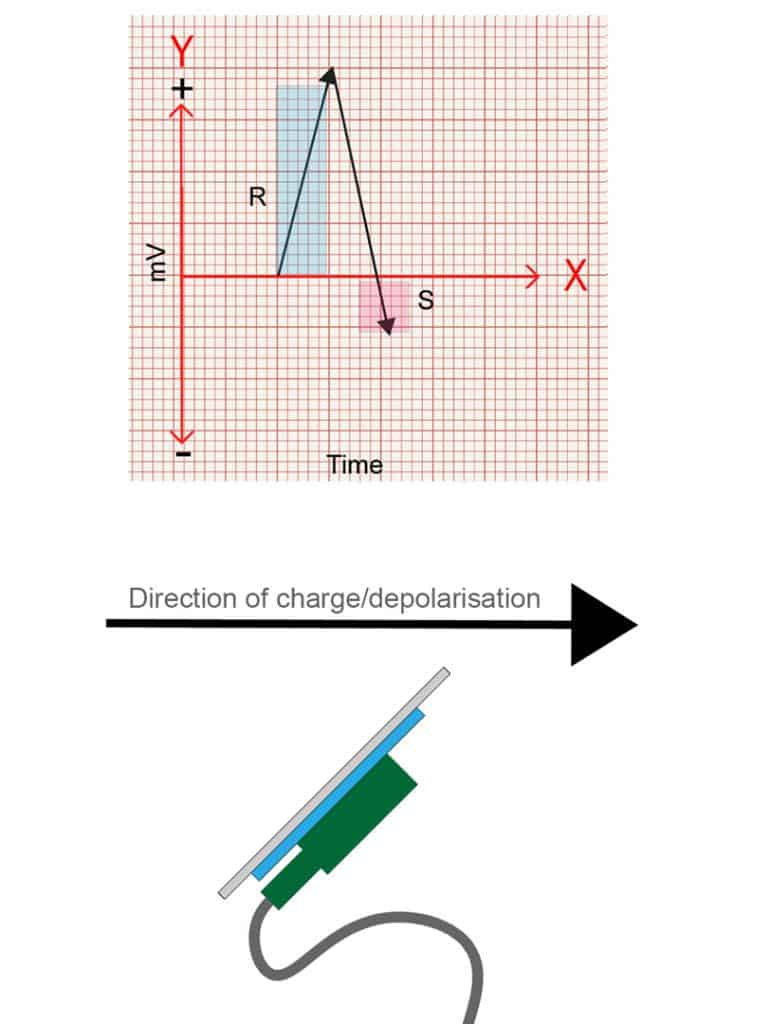
So, what happens if the charge moves at 45 degrees to an electrode’s position? Well, it’s a bit more towards the electrode than 90 degrees, but not straight on. So the tracing will show a predominately positive wave, with a smaller S wave. The opposite will be true if travelling at say 135 degrees away from an electrode.
Hopefully you can see then, that by varying the direction the charge travels, you’ll get different combinations of positive and negative deflections, and that it is relative to the position of each lead/view!
This means that the waves on an ECG not only have a value in magnitude (mV), but also direction. This combination of magnitude and direction is known as a vector.
So not only can the ECG waves tell you the charge in volts, but it can also show you the direction that charge is moving relative to the electrode placement.
Why is this important?
Well, many of the pathologies we come across effect the direction the charge moves across the heart.
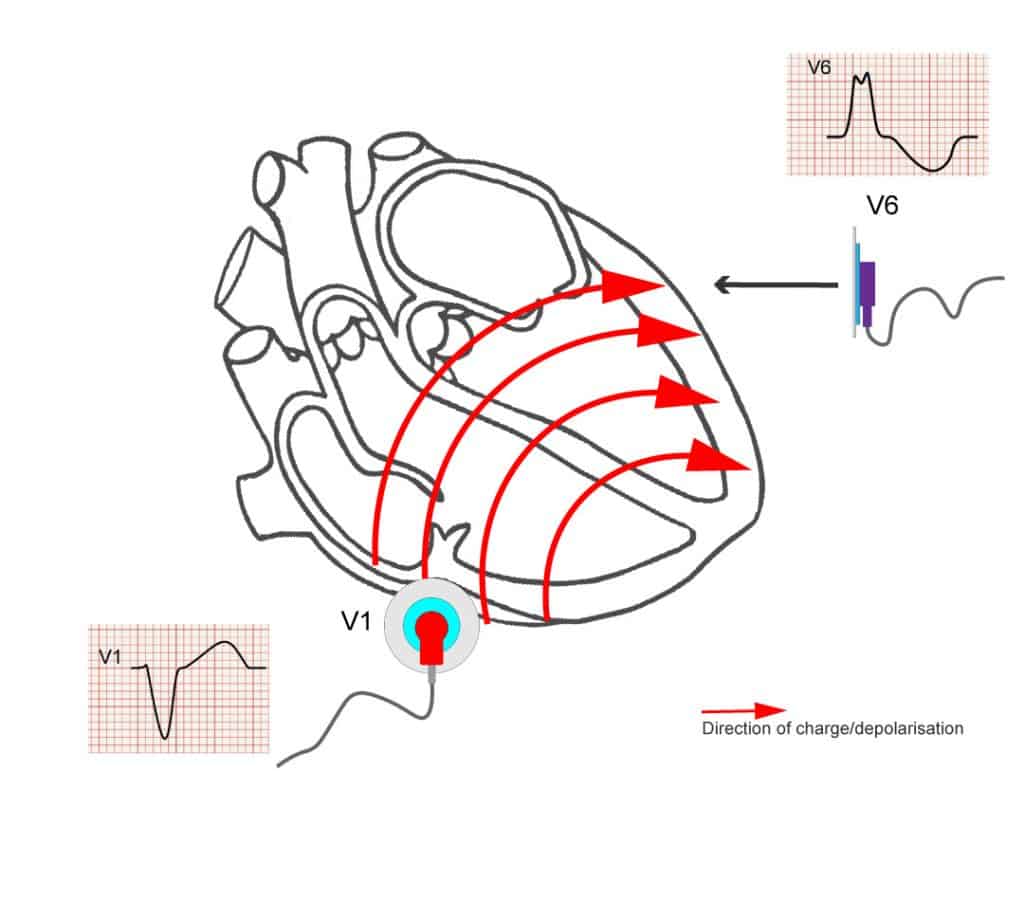
For example, in left bundle branch block (LBBB), the left conduction pathway is faulty. This means all of the electrical charge must come from the right side of the heart, and travels across the heart from right to left through the slower conducting muscle tissue.
V1 looks at the right side of the heart, so, with right to left movement, the charge is moving , slowly, away from V1, giving the classic negative, deep S wave seen in LBBB.
Understanding the concepts of vectors is important if you want to understand axis deviation, reciprocal changes in STEMIs, left anterior and left posterior fascicular blocks, T wave inversions and strain patterns, and how to identify bundle branch blocks.
Final Notes
So, to sum up, understanding how time is displayed on the ECG will lead to better recognition of conduction faults. Understanding that the ECG shows both direction and magnitude means you can easily understand how that charge is moving across the heart. Couple this with further reading around the physiology and pathophysiology and your ECG interpretation should greatly improve!
Just as a final caveat: electrophysiology is complicated. This is a basic description of the principles and vectors, but the images are not exact examples. The detailed process of how the electrodes work, how the leads form their views, the physics behind it and so on are far beyond the scope of this article, but hopefully this has given some insight into the applied nature of ECG.
References
The above post is written by an Article999 contributor and contains a mix of original content and explanations based on the below sources. All images are combined from licensed Adobe Stock images and the author’s own work, as with all Article999 content.
Earlier this year I had the pleasure of speaking with a patient with Functional Neurological Disorder (FND). Ailsa reached out to the College of Paramedics after experiencing an unsettling mixture of treatment by healthcare professionals in a variety of settings. She hopes to encourage healthcare clinicians to learn more about her condition, a functional neurological disorder. Our understanding of this group of conditions is currently being reshaped, so I agree it is another area in which we must stay up-to-date.
The publication of this post on Article 999 comes at a timely moment as just two days ago I read here that a study published in Epilepsy and Behaviour has documented MRI changes in patients with functional seizures. This furthers the point that what science and medicine thought it knew about this – and perhaps other conditions – while not fiction, is also not yet fact.
Members of the College of Paramedics can read the published article in last month’s issue of Paramedic INSIGHT or online here.