
FAST FACT – This is based on the Burns: The Practical Stuff video and post.
Full reference available in full post.
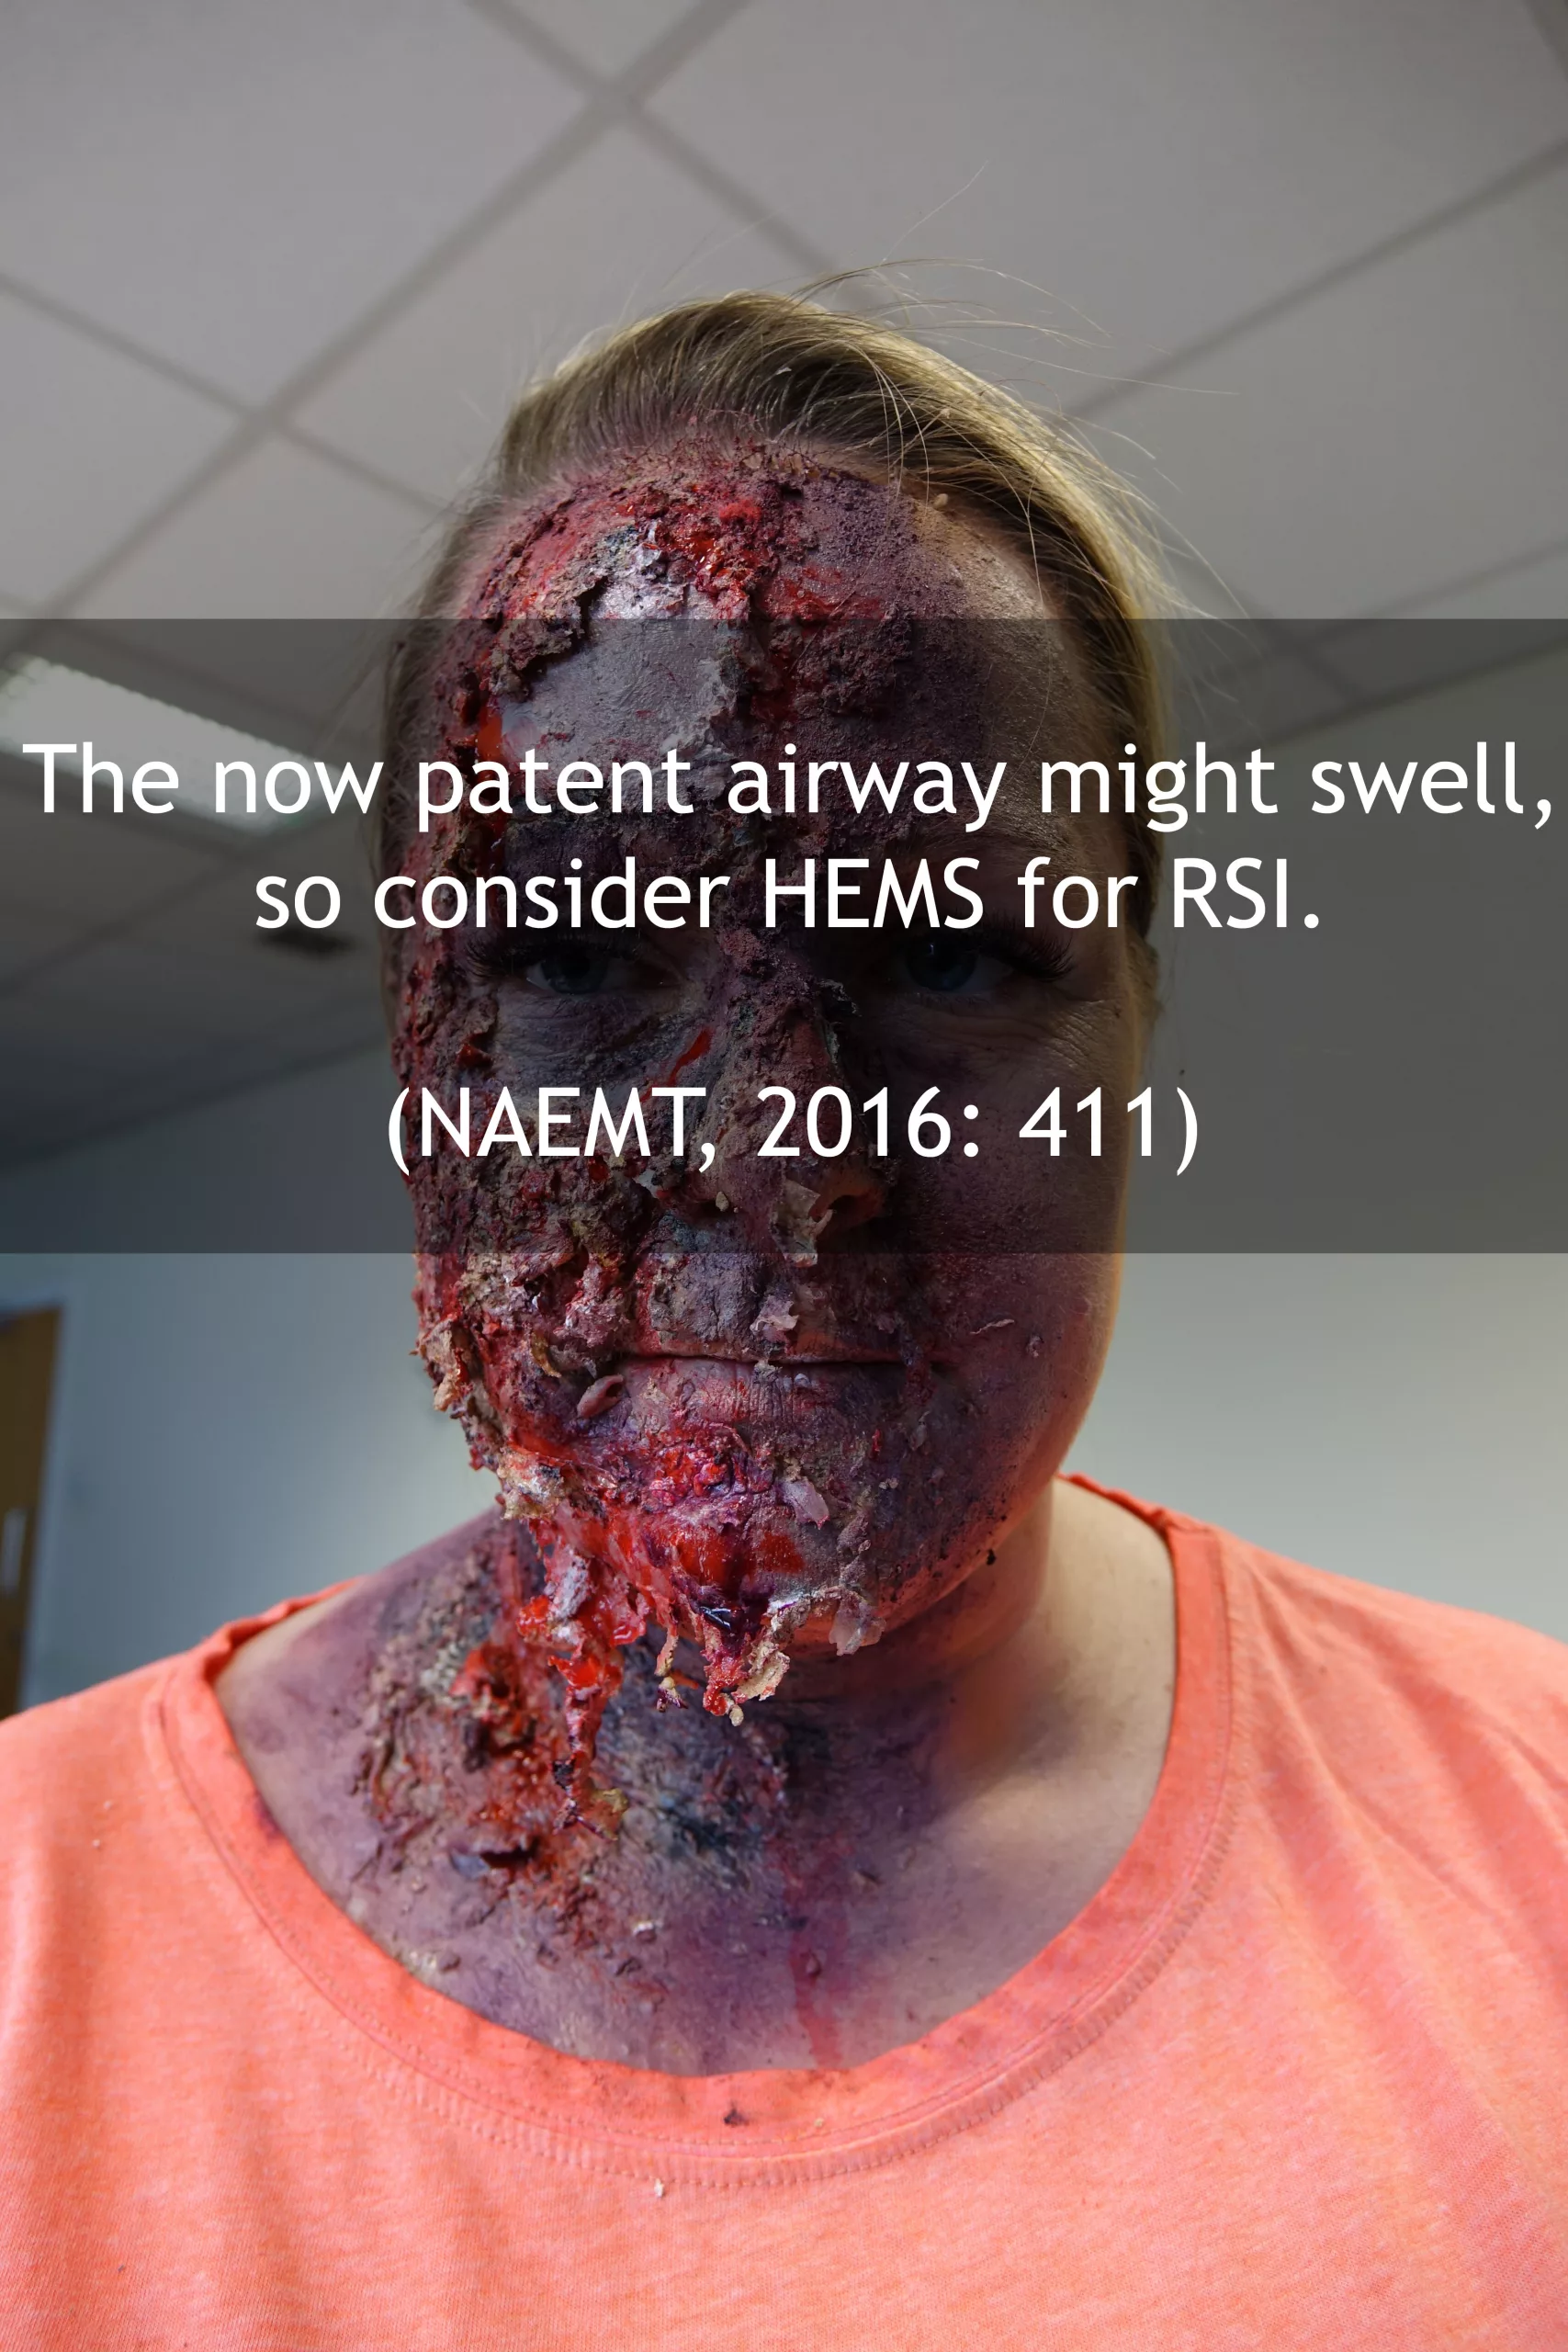
FAST FACT – This is based on the Burns: The Practical Stuff video and post.
Full reference available in full post.

The first video in the series is Ventilator V2, which was posted some time ago on the website & on YouTube. You may view the original video & more information here.
Please follow this link to view the quiz:
https://ed.ted.com/on/RyhGsz57
You may now complete a quiz to test your knowledge instead of or as well as watching the entire video. Each wrong answer will optionally link you to the relevant part of the video.


These videos should add to a resource that provides information that is easy to find and quick to learn from. Importantly, all of our videos have been produced based on publicly available information that is referenced, and all of them have been created by and for operational staff in the UK.
Feedback is welcome. As with all of our content, please remember to check local guidelines and read our full disclaimer before putting into place anything you see or read here.
Presenting one of our videos, I Gel: Why, What, When, How?

[restabs alignment=”osc-tabs-left” pills=”nav-pills” responsive=”false” tabcolor=”#6ad61d”]
[restab title=”Full Summary and Reference” active=”active”]
- Remember to follow ATLS protocol [and/or your local guidance and JRCALC guidelines]
- Use cervical spine control along with effective airway management
- ‘The most common critical care errors are related to airway and respiratory management. Gruen et al studied 25 trauma mortality patients […] [and] found that failure to intubate, secure or protect the airway was […] responsible for 16% of inpatient deaths’ [and that was in a trauma centre, albeit in 1996-2004!] (Gruen et al, 2006)
These, from the top of the head downwards, can be summarised as:
Head and soft tissue trauma
– These risk ‘delayed airway compromise’
Nasal bleeding/open wounds causing obstruction
Mandible fractures
– Leading to the tongue to drop back, blocking the oropharnyx
– Leading to blockage of the nasopharnygeal airway
Mouth obstructions
– From loose items & bodily fluids
Tracheal trauma
– Leading to swelling and displacement of essential airway structures behind them.
C-spine injury
– Leading to the need for “in-line stablization”. This can cause a reduced view during intubation
– The act of intubating might increase neck movements, potentially worsening this injury
Stomach
– [All patients ambulance personnel intubate in the prehospital environment might realistically have a full stomach]
– Note the risk of regurgitation
– Consider cricoid pressure – but also consider that this might ‘worsen the larnygeal view’
– Other tips noted in this section are not relevant to UK paramedics. Please read the full article for more information
These cause:
– Difficulties fitting a mask
– Less ‘efficient air transferring from the mask to the lungs’
– A ‘difficulty in visualizing the vocal cords’ when intubating due to fluids & obstructions
Gruen, R.L. et al. 2006. Patterns of Errors Contributing to Trauma Mortality: Lessons Learned from 2594 Deaths, Annals of Surgery, 244 (3): 371-380, Available Online:
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC1856538/
Krausz, A. et al. 2009. Maxillofacial trauma patient: coping with the difficult airway, World Journal of Emergency Surgery, 4: 21, Available Online: https://wjes.biomedcentral.com/articles/10.1186/1749-7922-4-21
[/restab]
[restab title=”Article 999 Super Summary”]
Head and soft tissue trauma, nasal bleeding or open wounds, mandible fractures, mouth obstructions, tracheal trauma, c-spine injury and the patient’s stomach contents can all make airway management more challenging (Hutchinson et al, 1990 in Krausz et al, 2009).
Top tips?
(Krausz et al, 2009)
[/restab]
[/restab][/restabs]


According to research by Khosraven et al (2015) one of the main disadvantages of an OP airway is that its length, shape & lack of an inflatable cuff may cause oxygen to leak, leading to less oxygen than we might hope for entering the patient’s lungs.

Or:
– What are the landmarks for Needle Cricothyroidotomy (Needle Cric)?
The cannula should be inserted ‘into the trachea via the cricothyroid membrane’ (Gregory & Mursell, 2010: 28).
Or:
When do you use a nasopharygeal airway?
‘…in the presence of trismus, an intact gag reflex, or oral trauma’ (Gregory & Mursell, 2010: 7)
Gregory, P. and Mursell, I. (2010) Manual of Clinical Paramedic Procedures, Sussex: John Wiley & Sons
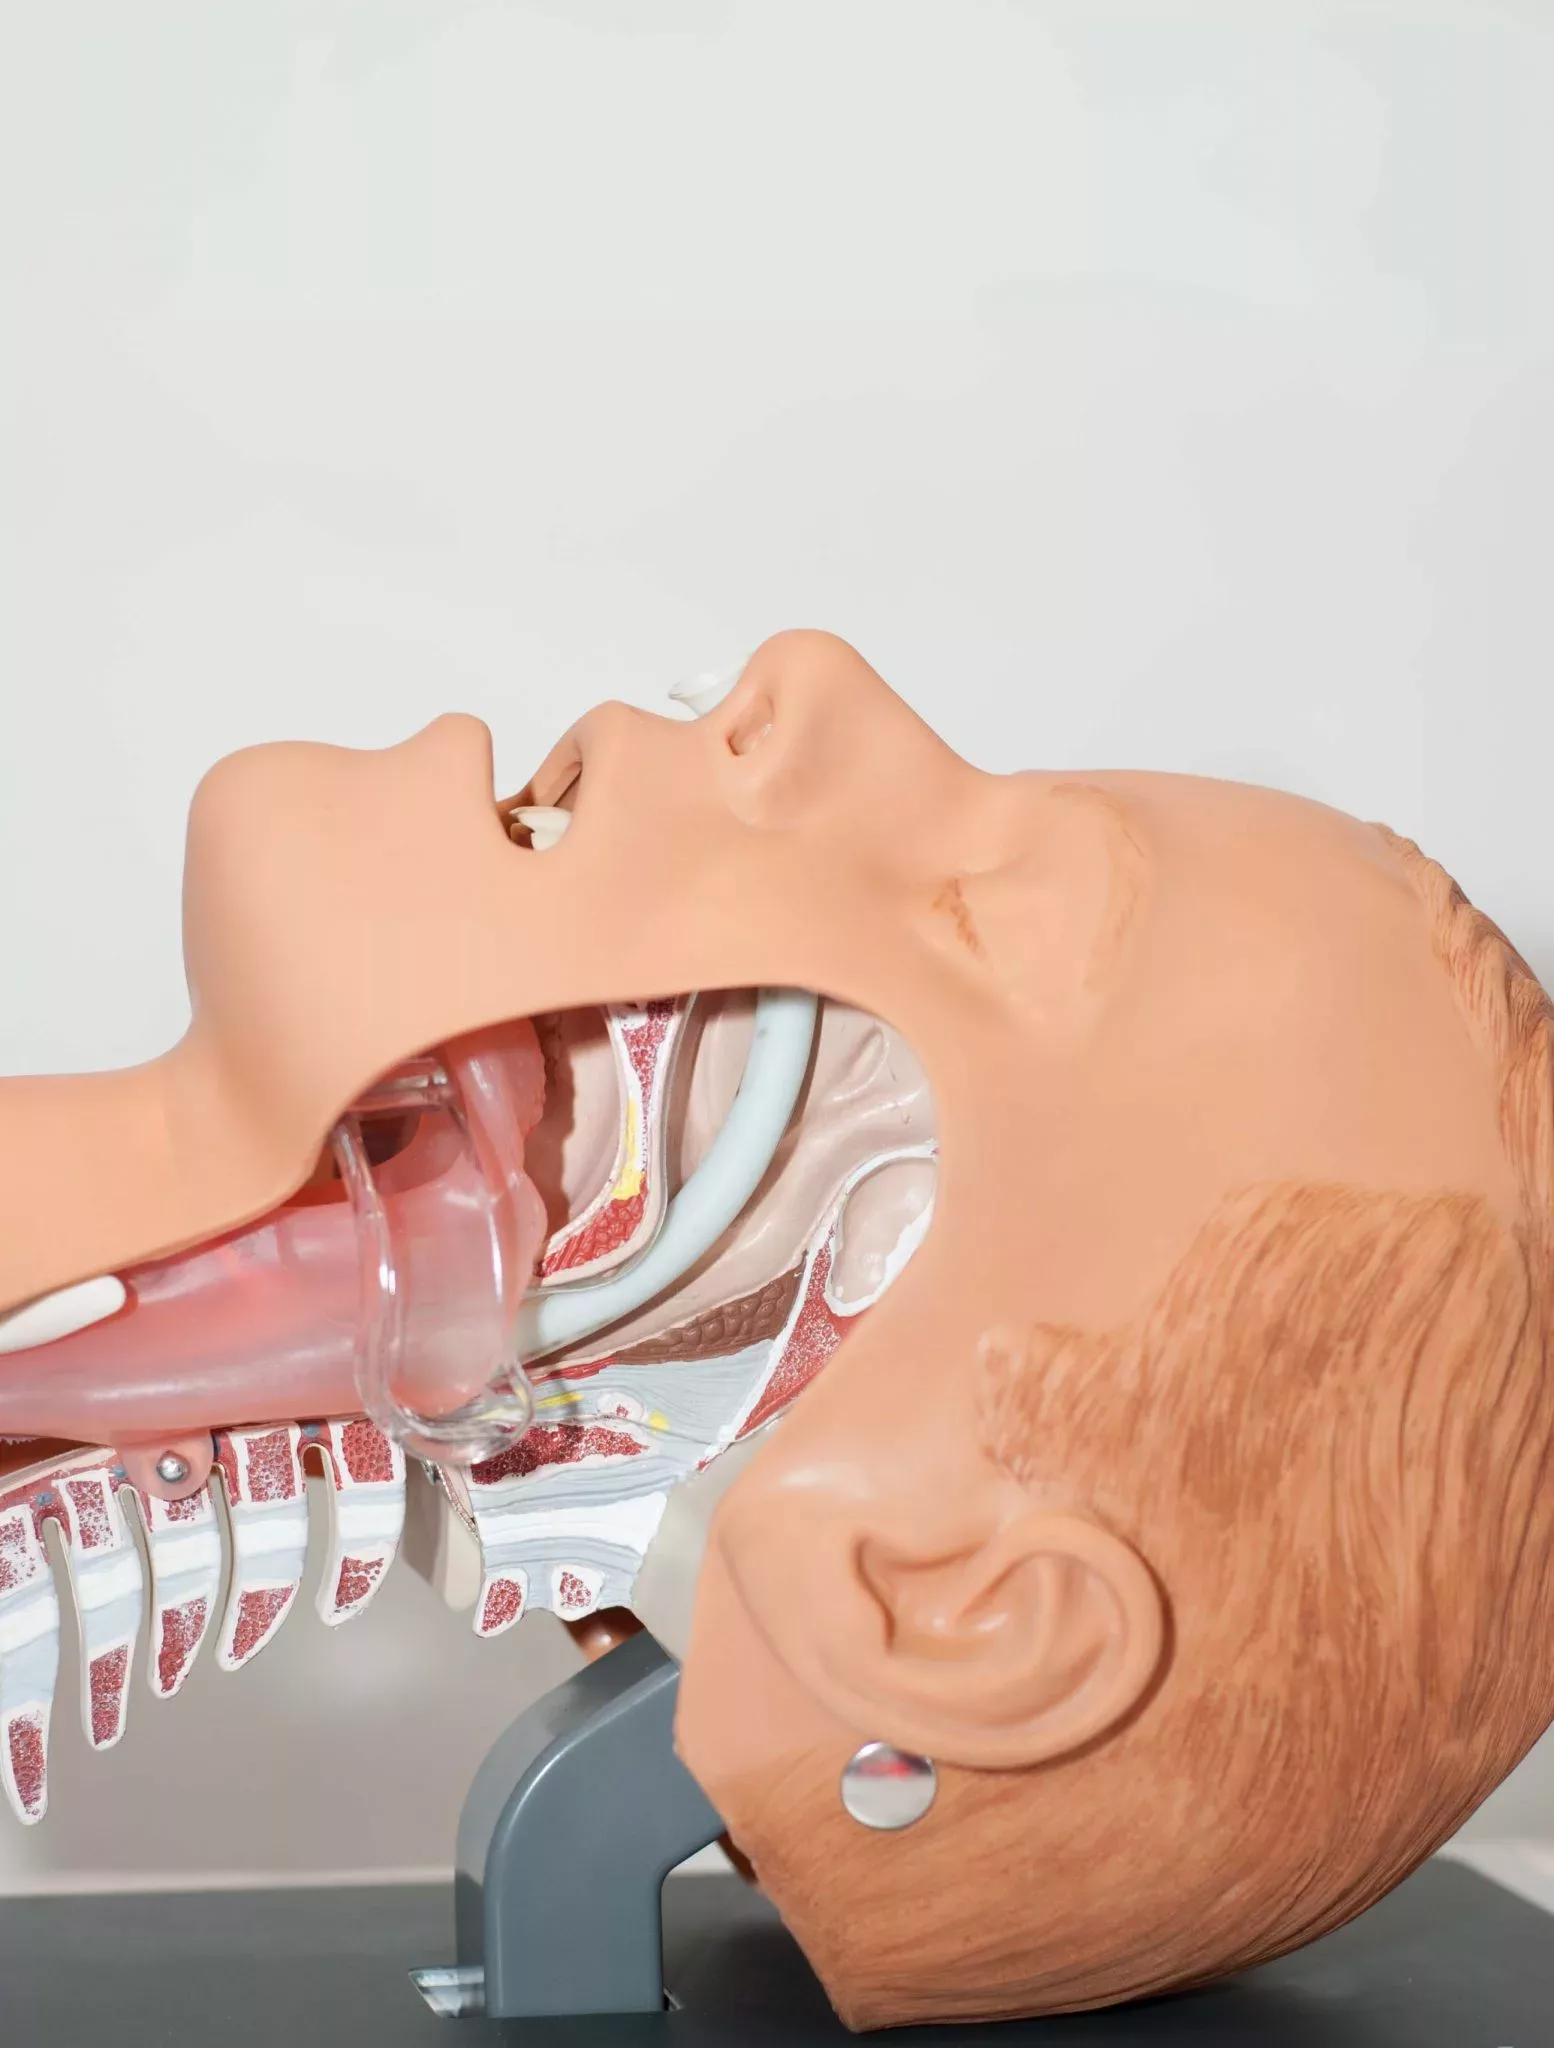
These ‘may occur at any level from the nose to the trachea’ but are commonly found ‘at the level of the pharynx’ (Gregory & Mursell, 2010: 2)
Gregory, P. and Mursell, I. (2010) Manual of Clinical Paramedic Procedures, Sussex: John Wiley & Sons
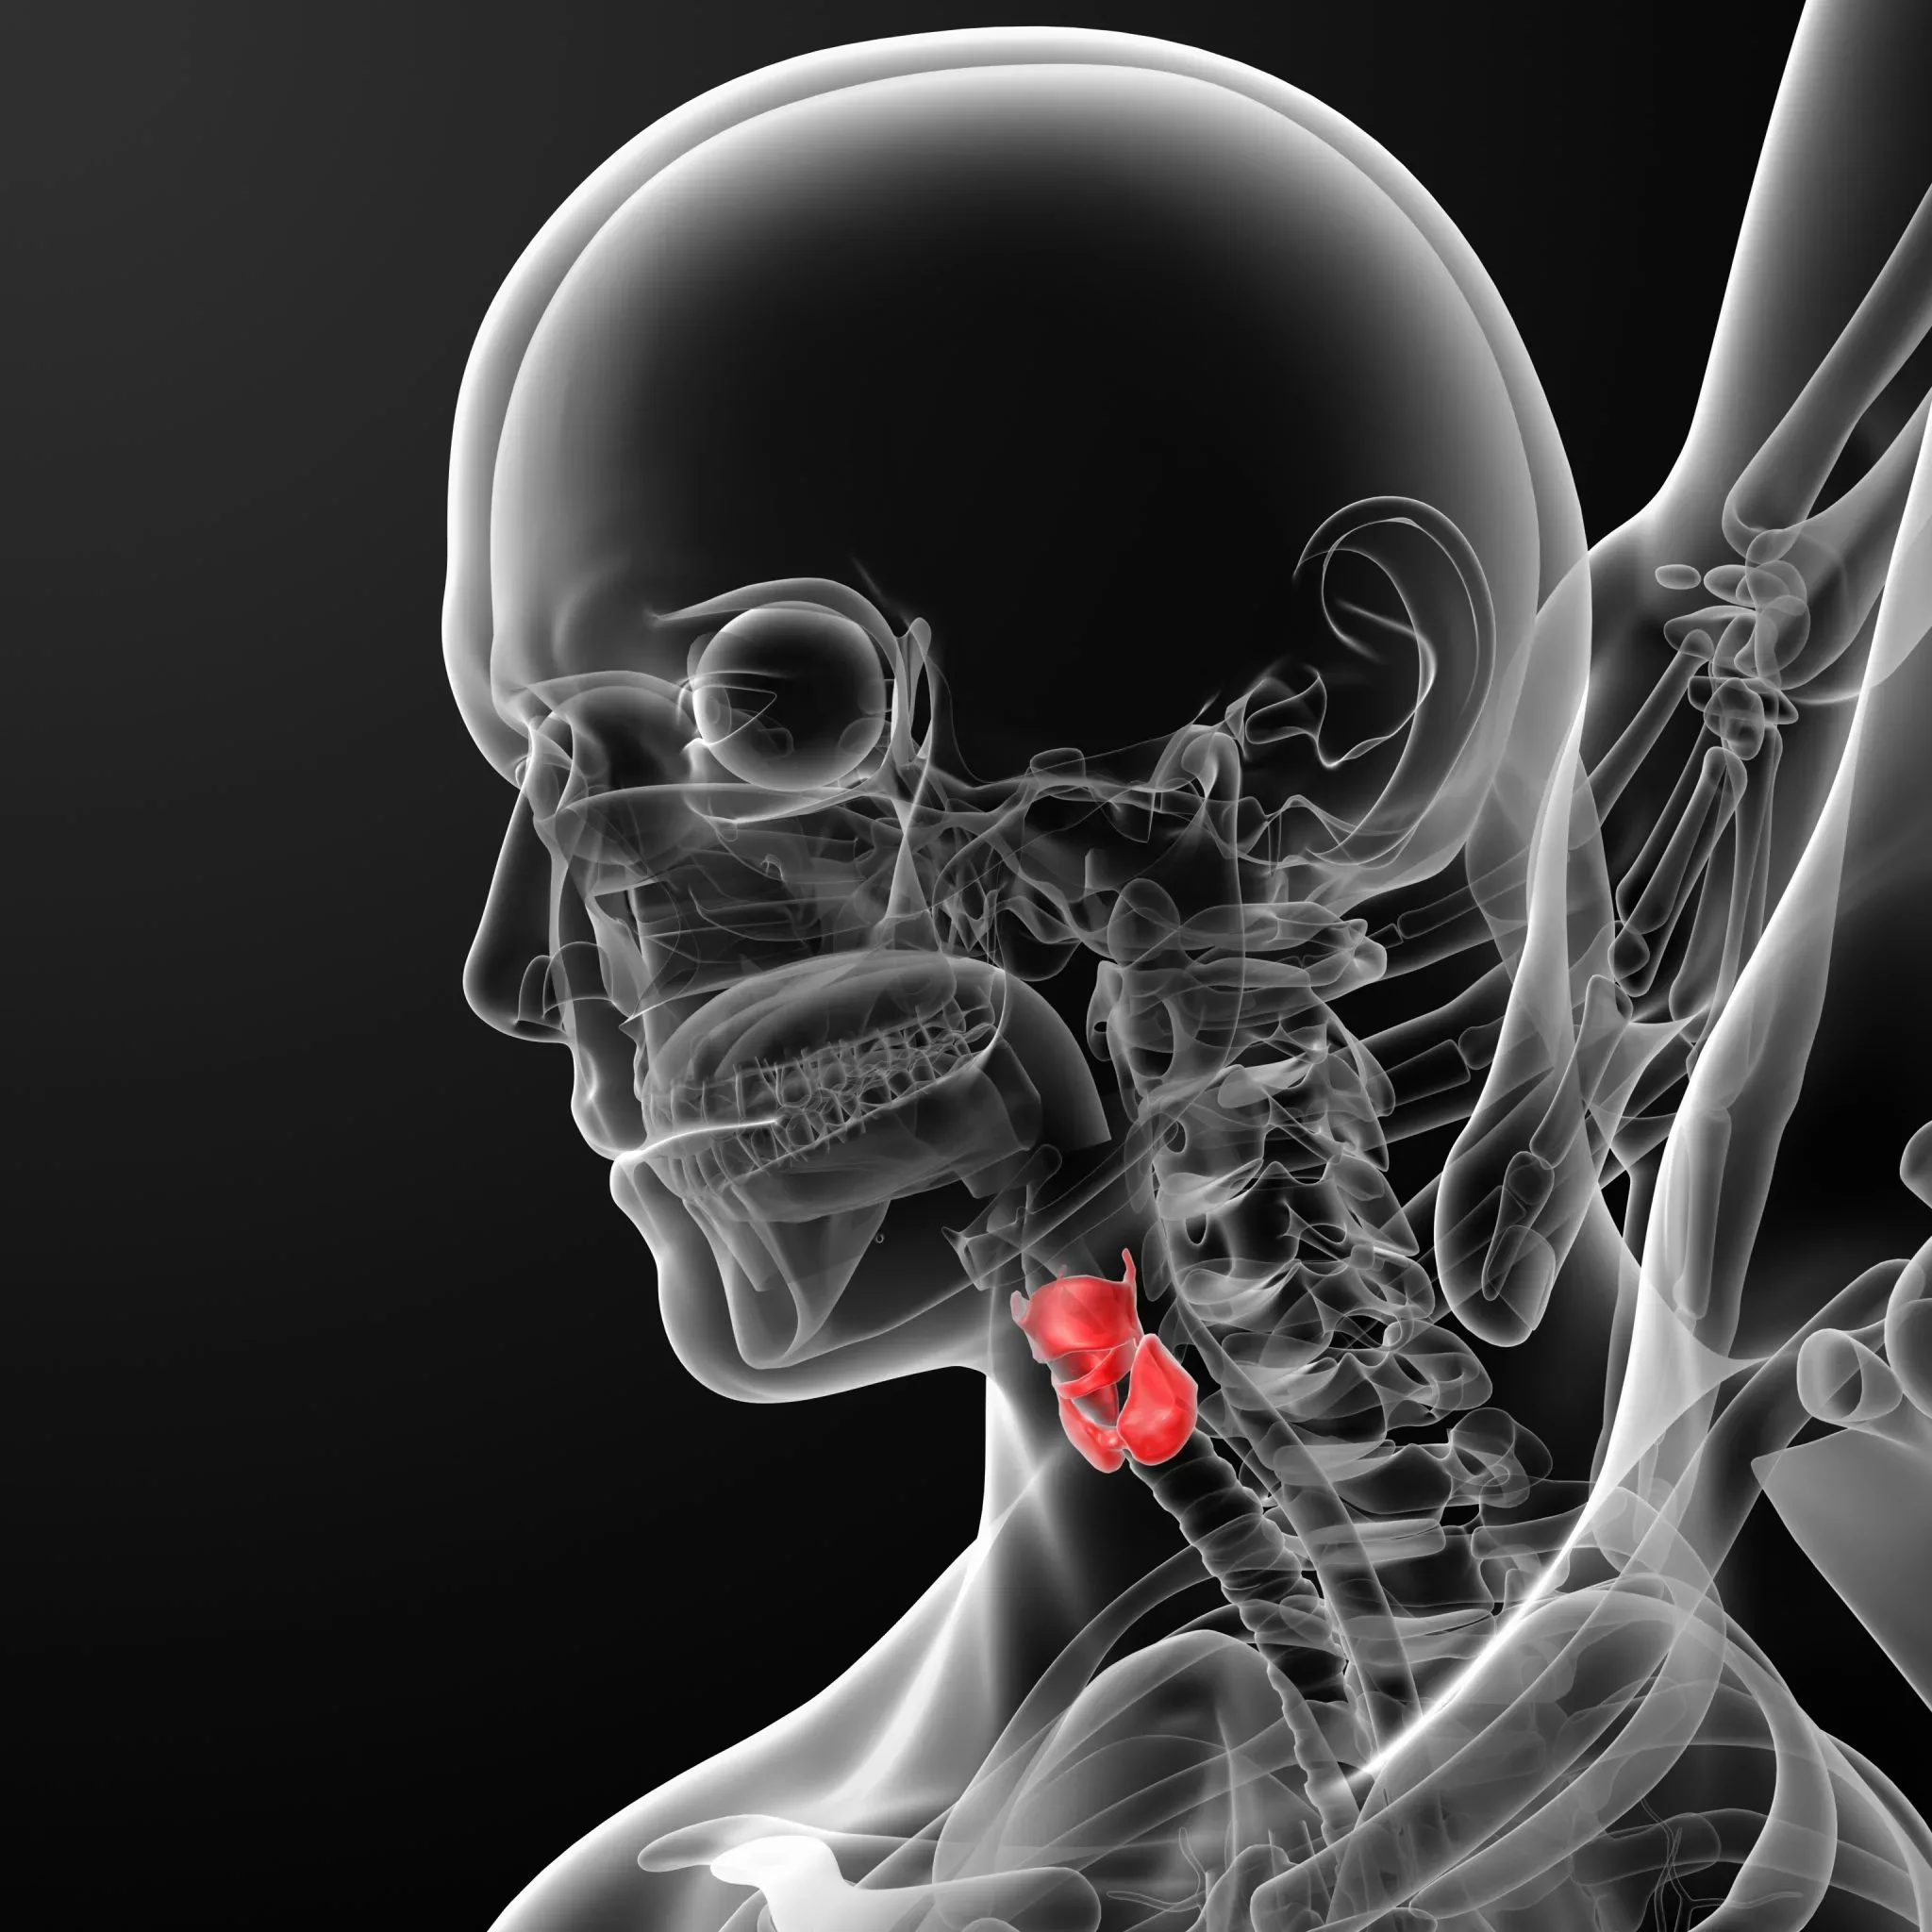
(Gregory & Mursell, 2010: 2)
Gregory, P. and Mursell, I. (2010) Manual of Clinical Paramedic Procedures, Sussex: John Wiley & Sons

